bg image
bg image

Serving Petersburg & Virginia

Cut admin drag on Petersburg care teams before 2026 budgets lock

Petersburg providers lose hours every shift to charting, referral chase, and prior-auth paperwork. That backlog delays patients and burns experienced staff. We build Healthcare AI that removes busywork while your clinicians stay in control of decisions. It is built for hospitals, specialty groups, and multi-site practices across the Tri-Cities. You get clear scope, fixed milestones, and cost visibility before development starts. Get Healthcare AI cost estimate in 24 hours. Tell us your stack, dataset access, budget band, and target go-live window.

Discuss Project

Overview

Why Petersburg clinics stall on AI projects in 2026

Petersburg sits between large health systems in Richmond and smaller independent practices in Colonial Heights, Hopewell, and Prince George. Leaders here face the same pressure: fewer staff, rising documentation load, and payers who demand cleaner claims. Manual workarounds do not scale when a single missed prior auth delays procedures for a week. Teams need systems that draft, route, and audit work without putting protected health information at risk.

Trusted Healthcare AI Partner for Petersburg Businesses. We work with US-based clients, including companies operating in Virginia. Our work starts from operational bottlenecks you can measure today, not from a model demo. We map intake, coding support, referral tracking, and patient messaging before any training run. That order keeps spend tied to throughput and denial rates instead of novelty.

Technical delivery favors retrieval over blind generation when records must stay accurate. We have shipped an internal support agent that answers employee questions with enterprise search and retrieval-augmented replies, plus workflow automation around those answers. The same pattern fits clinical policy lookup and staff onboarding when boundaries and audit logs are required. For scoring and feedback tasks we used rubric-based evaluation so outputs stay consistent at volume. Petersburg groups can apply those patterns to coding assist, chart completeness checks, and quality review queues.

Integration remains the hard part for legacy EHRs common across Southside Virginia. We isolate PHI in controlled stores, enforce least privilege, and design fail-safe handoffs so a model error never silently changes a medical record. Security reviews, access logs, and human approval gates ship with the first release. That approach reduces rework when compliance officers join the project midstream.

If you already explored computer vision for imaging workflows, the same delivery discipline applies to text and process automation. Expect a written data map, risk register, and MVP scope within the first two weeks. Across the US market we have delivered 10+ AI projects that emphasize retrieval, structured evaluation, and workflow automation rather than open-ended chat. Nearby facilities in Chester and Dinwiddie often join multi-site rollouts once the first clinic proves cycle-time gains.

Talk to an Expert
Bottleneck mapping

Bottleneck Mapping First

Intake, coding support, referral tracking, and messaging timed before any model work

Retrieval-first delivery

Retrieval Over Generation

Enterprise search + RAG with citations for policy lookup and chart assist

PHI isolation

PHI-Safe Integration

Controlled stores, least privilege, audit logs, and human approval gates

Rubric evaluation

Rubric-Based Evaluation

Consistent scoring for coding assist, completeness checks, and quality queues

Architecture for regulated care

HIPAA-bound agent stacks Petersburg teams can operate

Petersburg health groups receive a production stack built for auditability first. Core pieces are a private retrieval layer over approved clinical and operational documents, task-specific agents with constrained tools, and workflow hooks into the systems staff already open each morning. We separate identity, data access, and model calls so a single misconfigured key cannot expose charts. Every answer carries source citations and a confidence threshold that routes low-trust outputs to a human queue.

We ground architecture in systems we have already shipped. For enterprise employee support we built an LLM agent with enterprise search, retrieval-augmented answers, and workflow automation so staff could resolve policy questions without ticket ping-pong. Healthcare operations face the same pattern: nurses and revenue-cycle staff need grounded replies, not creative prose. For assessment tooling we delivered automated scoring with rubric-based evaluation and feedback generation, which maps cleanly to coding quality checks and chart completeness scoring where criteria are explicit.

Security/compliance is enforced in design, not bolted on at go-live. PHI stays in region-restricted stores with encryption at rest and in transit. Role-based access mirrors your directory groups. Prompts and completions log to immutable audit trails that compliance can export without engineering help. We avoid training foundation models on your records unless a separate BAA-covered agreement and de-identification plan exist. Preferring retrieval plus light adapters keeps residual risk lower than fine-tuning on raw notes.

DevOps for these systems means staged releases, canary cohorts, and rollback that does not strand in-flight cases. Infrastructure as code defines networks, secrets, and queue workers so environments match. Observability covers latency, tool-call failures, retrieval miss rates, and human override frequency. Cost controls cap token spend per department and alert when a workflow starts looping. On-call runbooks name who freezes automated actions if a model drift signal appears during a busy clinic day.

Integration adapters speak HL7 or FHIR where available and fall back to secure file drops or RPA only when APIs are closed. We document each mapping with sample payloads so your internal IT can maintain the boundary after handoff. Model choice favors vendors and open weights that accept private networking and clear data retention terms. Evaluation harnesses replay de-identified case sets before traffic shifts. The result is a system your clinical operations lead can explain to a board without marketing language.

plavno logo

Build your first
Smart AI project today!

Just tell the Plavno AI Agent about your project - it will ask questions, gather requirements, and propose a tailored solution

Readiness path

From paper-heavy intake to assisted workflows

A maturity sequence for Petersburg providers who must prove value before buying more automation. Each stage produces artifacts finance and compliance can review.

Clipboard
Team
01

Step 1: Manual baseline capture (1–2 weeks)

We time real shifts in Petersburg clinics and count touches on referrals, prior auth, and chart closure. Staff interviews separate policy constraints from habit. You receive a baseline report with cycle times, error types, and volume by site. No model work starts until the numbers exist. This phase also flags incomplete data sources that would poison later training. Timeline is one to two weeks for a single specialty line.

02

Step 2: Assisted drafting pilots (2–3 weeks)

Operators keep full control while models draft notes, replies, or coding suggestions inside a side panel. Every suggestion shows sources and requires accept or edit. We log edit distance so quality is measurable. Training for the pilot cohort happens on-site or remote within the Tri-Cities schedule. Success means reduced keystrokes without rising correction time. Expect two to three weeks including policy review.

Search in doc
Rocket
03

Step 3: Routed automation with gates (3–4 weeks)

Approved workflows move from draft-only to conditional send when confidence stays high and rules pass. Exceptions still land with humans. We add SLA timers so stalled cases surface before patients notice. Monitoring covers override rates and payer rejection codes tied to automated steps. Change control freezes prompt edits outside release windows. Typical duration is three to four weeks after pilot sign-off.

04

Step 4: Cross-site autonomous lanes (4–6 weeks)

Stable lanes expand to Colonial Heights or Hopewell sites once Petersburg metrics hold for a defined period. Role templates, vocabularies, and payer rules become shared assets. Local leads keep kill switches. Cost dashboards show spend per encounter type. Quarterly reviews decide which new processes enter the same path. Plan four to six weeks per additional site depending on EHR variance.

Delivery capabilities

What Petersburg operations leaders actually receive

Clinical document retrieval

Clinical document retrieval

Staff waste minutes hunting policies and prior notes during crowded Petersburg clinic hours. We stand up a private search index over approved PDFs, intranet pages, and structured extracts. Retrieval-augmented answers cite passages so supervisors can verify. Enterprise search patterns we used for internal knowledge agents keep replies tethered to sources. Access follows directory roles already in place. Updates to source libraries reindex on a schedule you control.

Rubric-based quality scoring

Rubric-based quality scoring

Inconsistent chart reviews create surprise denials for Virginia payers. Automated scoring with explicit rubrics flags missing elements before submission. Feedback generation explains the gap in plain language for new coders. We chose structured evaluation because open-ended critique drifts. Thresholds route low scores to senior review only. Trends feed training plans for Southside clinics.

Workflow automation bridges

Workflow automation bridges

Even good AI fails if results die in an inbox. We connect agent outputs to ticketing, EHR tasks, or secure messaging with clear ownership. Workflow automation from our enterprise agent work prevents orphaned suggestions. Retries and dead-letter queues protect busy days. Auditors see who approved each automated move. Petersburg multi-site groups can share templates without sharing PHI databases.

HIPAA boundary design

HIPAA boundary design

Regulated data cannot ride consumer chat tools. We design encryption, logging, and BAAs as first-class requirements. Network isolation and key management prevent casual exports. Prompt filters block accidental bulk dumps of identifiers. Incident playbooks name Virginia contacts and timelines. Reviews happen before production traffic, not after a scare.

Cost and drift controls

Cost and drift controls

Token bills surprise teams that lack caps. Department budgets, caching of frequent retrievals, and smaller models for routine steps hold spend steady. Drift checks compare current outputs with gold sets each week. Alerts fire when override rates climb. Finance gets a simple reprint of unit cost per automated encounter. That clarity matters when Chester and Petersburg sites share a contract.

Case Study

We help customers cut
down on development

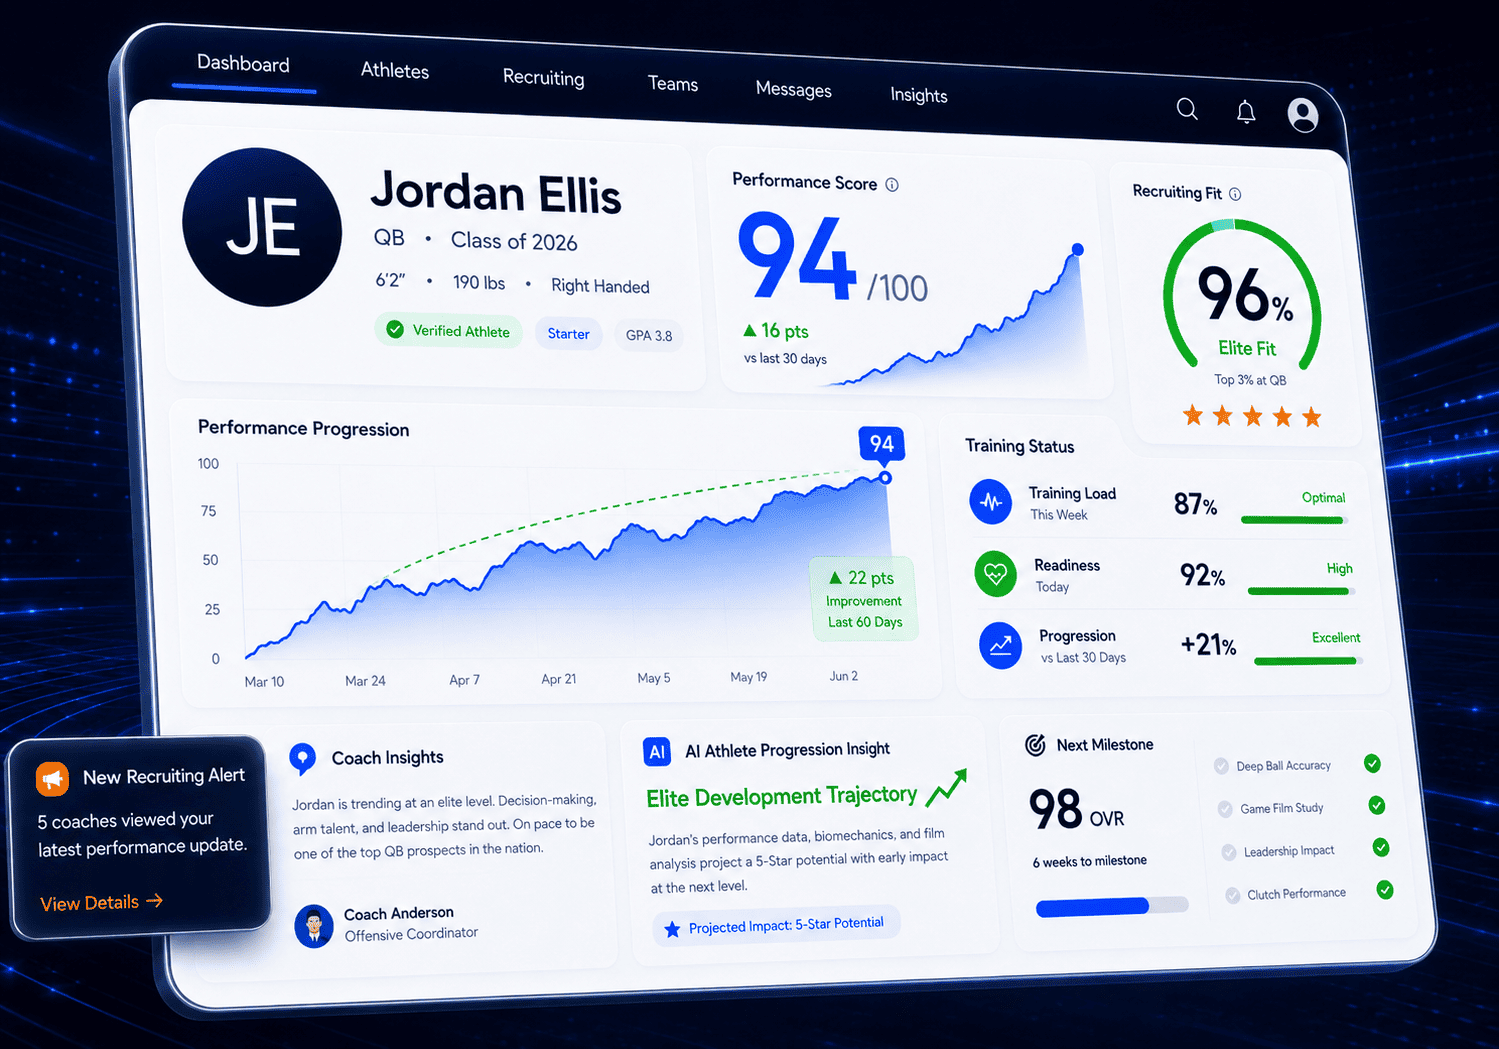
AI-Powered Sports Performance & Recruiting Platform for Virginia Clubs, Academies & Youth Programs

Plavno developed a custom sports technology platform for Virginia-based clubs and academies to combine athlete performance tracking, coach communication, recruiting workflows, and mobile engagement in one ecosystem.

Read More
3x

faster recruiting pipeline

AI-Powered Sports Performance & Recruiting Platform for Virginia Clubs, Academies & Youth Programs

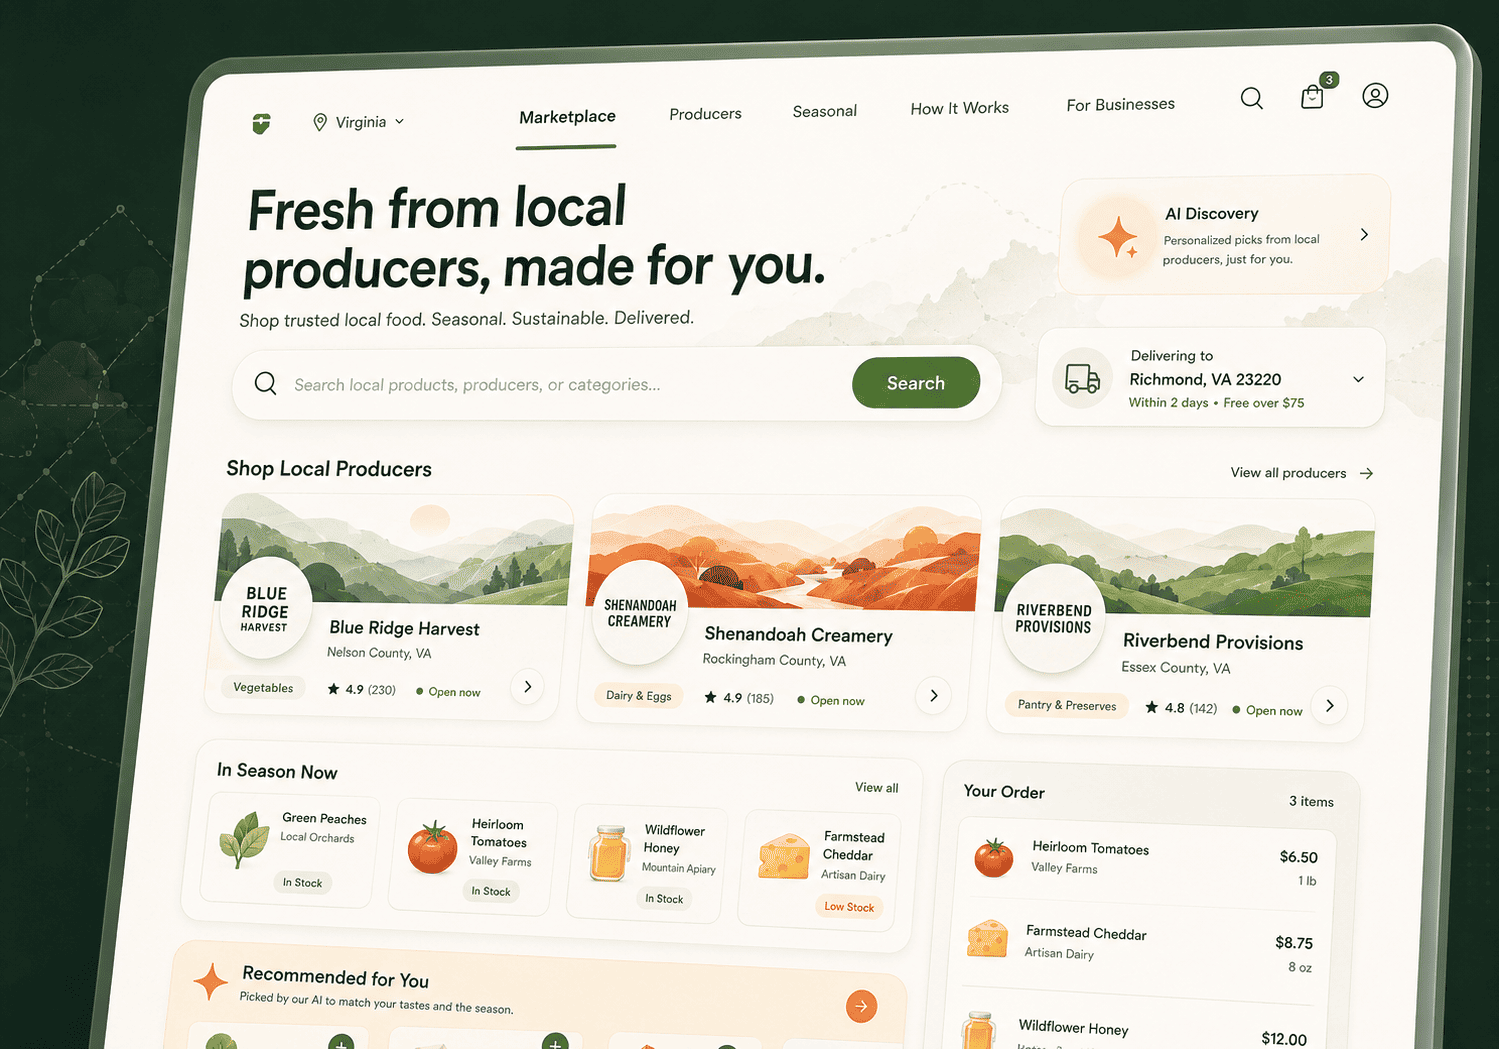
Digital Marketplace for Virginia Farmers, Local Producers & Direct-to-Consumer Food Sales

Plavno developed a custom multi-vendor marketplace for Virginia-based farmers, food producers, and regional sellers to unify product listings, vendor operations, customer ordering, and local fulfillment workflows.

Read More
3x

increase in product discovery relevance

Digital Marketplace for Virginia Farmers, Local Producers & Direct-to-Consumer Food Sales

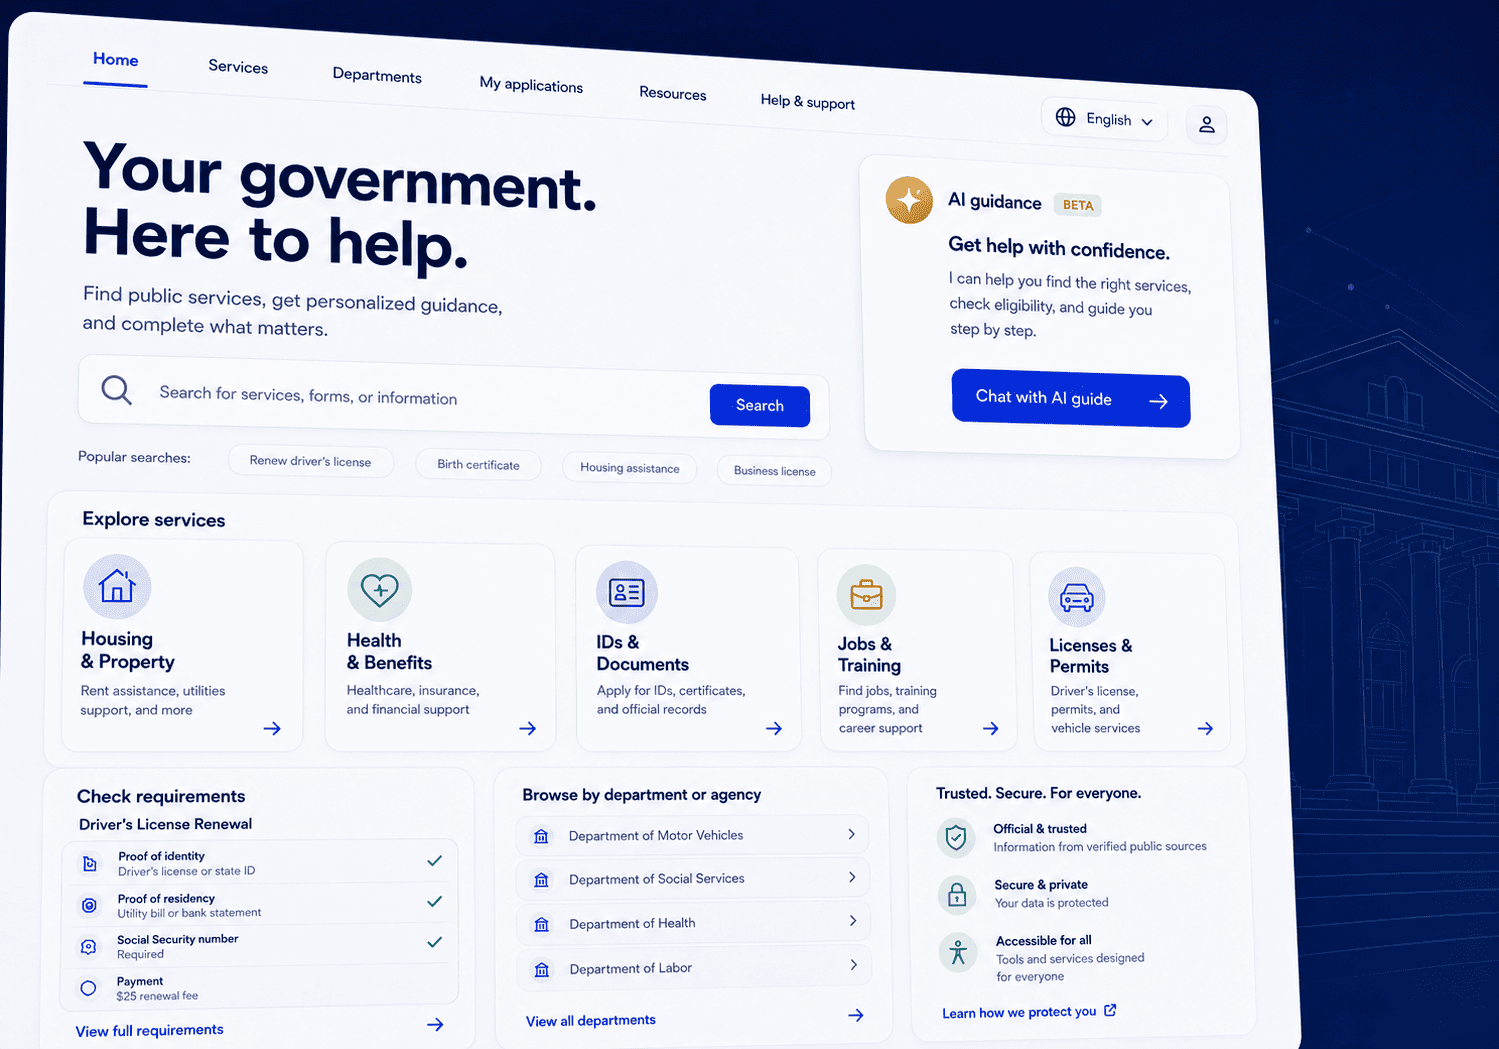
AI-Powered Citizen Services Website Platform for Virginia State Agencies

Plavno developed a modern eGovernment website platform for Virginia state agencies that centralizes citizen services, public information, department content, and an AI-powered guidance agent in one scalable system.

Read More
70%

reduction in routine citizen inquiries to agency staff

AI-Powered Citizen Services Website Platform for Virginia State Agencies

Healthcare AI Solutions for Petersburg Industries

Where Tri-Cities operators reclaim hours in 2026

Use cases map to real Petersburg, Colonial Heights, and Hopewell workloads. Each item ties a local pain to a concrete automation pattern.

Revenue Cycle

Revenue Cycle

Claims Assist

Hospital revenue cycle assist

Petersburg hospitals fight rising denial rates on incomplete packages. Agents assemble documentation checklists from payer rules and flag gaps before claim drop. Staff correct once instead of chasing months later. Technical path uses retrieval over policy PDFs plus rubric scoring on required fields. Teams report faster first-pass yield when exceptions shrink. Target ROI is fewer days in A/R rather than headcount cuts. Human approval remains mandatory on high-dollar claims.

Referral Intake

Referral Intake

Specialty Clinics

Specialty clinic referral intake

Ortho and cardiology groups near Fort Lee lose referrals to slow scheduling back-and-forth. Automation extracts key data from inbound faxes and portal forms, then opens structured tasks. Missing films trigger patient messages with fixed templates. Workflow automation routes urgent cases by rule. Clinics reduce idle slots without hiring after-hours clerks. ROI shows as filled schedules within one billing cycle. PHI stays inside approved connectors only.

Shift Handoff

Shift Handoff

Care Notes

Long-term care shift handoff

Facilities in Dinwiddie and Prince George suffer omissions when overnight notes stay unstructured. Assistive drafting summarizes events against a facility rubric and highlights vitals outliers for the incoming nurse. Retrieval pulls care-plan sections so summaries stay grounded. Overrides teach the system which phrasings matter. Better handoffs lower preventable escalations. Measured value is fewer morning recovery calls to physicians. Devices remain out of clinical decision authority.

Outreach Queues

Outreach Queues

Public Health

Public health outreach queues

City and county programs juggle multilingual outreach with thin staff. Classification models sort inbound messages by urgency and topic, then draft compliant replies for human send. Rubric checks block casual medical advice in automated drafts. Logging supports grant reporting without extra spreadsheets. Throughput gains free nurses for field work. Cost savings appear as reduced overtime during seasonal surges. Integration favors existing CRM tools over new portals.

Occupational Health

Occupational Health

Clearance

Employer occupational health

Manufacturers and logistics hubs around Petersburg need faster clearance visits and injury paperwork. Agents prefill visit packets from prior records and company protocol documents. Ballistic checks ensure required fields exist before clinician close. Employers receive status without unrestricted chart access. Cycle time from gate arrival to return-to-work note drops. ROI is reduced idle labor on the plant floor. Security isolates employer portals from clinical systems.

Behavioral Docs

Behavioral Docs

Notes

Behavioral health documentation

Outpatient behavioral practices in the Richmond-Petersburg corridor burn hours on notes after last sessions. Session assistants draft structured summaries from clinician bullets and validated templates. Rubric evaluation flags missing risk assessments before lock. No ambient recording ships unless contractual and technical controls pass review. Clinicians keep authorship and final edits. Recovered evening hours reduce burnout risk. Billing codes gain consistency when note structure stabilizes.

Engineering contrast

Why choose deep build over resold chat bots

Generic agencies drop a model into a website. We design retrieval, gates, and operations your compliance team can defend.

Generic Agencies
Our Platform (Deep Engineering Expertise)
HIPAA-oriented architecture from day one
checkmark
Retrieval with citations on every answer
checkmark
Rubric-based quality scoring before rollout
checkmark
Workflow hooks into existing EHR tasks
checkmark
checkmark
Token spend caps per department
checkmark
Slide deck strategy without shipping code
checkmark
Post-launch drift monitoring and freeze switches
checkmark

Testimonials

We are trusted by our customers

“They really understand what we need. They’re very professional.”

The 3D configurator has received positive feedback from customers. Moreover, it has generated 30% more business and increased leads significantly, giving the client confidence for the future. Overall, Plavno has led the project seamlessly. Customers can expect a responsible, well-organized partner.

Sergio Artimenia

Commercial Director, RNDpoint

Sergio Artimenia

“We appreciated the impactful contributions of Plavno.”

Plavno's efforts in addressing challenges and implementing effective solutions have played a crucial role in the success of T-Rize. The outcomes achieved have exceeded expectations, revolutionizing the investment sector and ensuring universal access to financial opportunities

Thien Duy Tran

Product Manager, T-Rize Group

Thien Duy Tran

“We are very satisfied with their excellent work”

Through the partnership with Plavno, we built a system used by more than 40 million connected channels. Throughout the engagement, the team was communicative and quick in responding to our concerns. Overall, we were highly satisfied with the results of collaboration.

Michael Bychenok

CEO, MediaCube

Michael Bychenok

“They have a clear understanding of what the end user needs.”

Plavno's codes and designs are user-friendly, and they complete all deliverables within the deadline. They are easy to work with and easily adapt to existing workflows, and the client values their professionalism and expertise. Overall, the team has delivered everything that was promised.

Helen Lonskaya

Head of Growth, Codabrasoft LLC

Helen Lonskaya

“The app was delivered on time without any serious issues.”

The MVP app developed by Plavno is excellent and has all the functionality required. Plavno has delivered on time and ensured a successful execution via regular updates and fast problem-solving. The client is so satisfied with Plavno's work that they'll work with them on developing the full app.

Mitya Smusin

Founder, 24hour.dev

Mitya Smusin

Engagement sequence

How a 2026 Petersburg build reaches production

Delivery phases emphasize decision gates, not endless prototyping. You always know budget remaining and the next exit option.

Clipboard
Team
01

Step 1: Scope and constraints lock (1 week)

We collect budget band, timeline, stack list, and dataset access rules in a single working session. Legal reviews BAA needs before engineering starts. Outcomes become measurable targets like chart close time or denial rate. Risks around data quality enter a written register. You leave with a priced MVP boundary. Timeline is one focused week including stakeholder sign-off.

02

Step 2: Data mapping and gold sets (2 weeks)

Engineers inventory sources, retention rules, and field definitions with your HIM lead. De-identified gold cases support evaluation before users see outputs. Connection prototypes prove that APIs or secure drops actually work. Gaps become either blockers or explicit out-of-scope notes. Clients receive a data readiness brief. Two weeks is standard when EHR documentation exists.

Search in doc
Rocket
03

Step 3: Build, evaluate, harden (4–6 weeks)

Agents, retrieval indexes, and workflow adapters land behind staging credentials. Rubric tests from our grader-style work enforce consistency on scoring tasks. Security review covers logs, keys, and PHI paths. Clinician champions run scripted scenarios and score usefulness. Only then does traffic expand. Four to six weeks covers a single high-value workflow family.

04

Step 4: Launch ops and transfer (2 weeks)

Production cutover uses canaries on one Petersburg unit first. Runbooks, dashboards, and freeze procedures transfer to your ops owner. Training videos and office hours cover night and weekend staff. We stay on rapid response for the initial window. Backlog for the next automation lane is ranked with measured ROI. Two weeks closes the formal engagement unless you extend support.

Eugene Katovich

Eugene Katovich

Sales Manager

Need a custom software solution? We’re ready to help!

Plavno has a team of skilled developers ready to tackle the project. Ask me!

Get a Free Quote

Before you buy

Vendor checks Petersburg buyers should finish first

  • Confirm BAA and data residency — Demand a signed business associate agreement written for your entity type. Ask where prompts, embeddings, and logs physically sit. Reject vague multi-region defaults for PHI. Require deletion SLAs when contracts end. Verify subprocessors against your risk list. Document who can approve emergency access. Keep evidence in the compliance binder before kickoff.

  • Inspect evaluation method — Ask how quality is measured beyond demo screenshots. Rubric-based scoring and gold sets beat anecdotal praise. Request sample failure cases and how they surface. Confirm humans stay in loop for clinical risk. Compare edit rates the vendor expects after go-live. Petersburg teams should refuse black-box accuracy claims. Record the metric definitions in the SOW.

  • Map EHR integration depth — List write actions the tool will attempt. Prefer RMS or FHIR writebacks monitored in staging. Avoid silent chart edits without dual approval. Clarify fallback when interfaces drop during outages. Measure latency on real clinic networks, not lab Wi-Fi. Involve local IT early for Colonial Heights satellite sites. Capture rollback steps in plain language.

  • Model cost controls — Require hard caps per department and alerting. Review caching strategy for repeated policy queries. Compare small-task models versus one large model for every action. Ask for monthly forecast mistakes the vendor made elsewhere. Align finance on unit cost per automated encounter. Include kill switches if spend spikes. Revisit caps after the first full billing cycle.

  • Post-launch ownership — Name who watches drift dashboards after warranty ends. Confirm how prompt changes are versioned and approved. Ensure night coverage exists for automated outbound messages. Schedule quarterly audits against new payer rules. Keep training materials for staff turnover common in Virginia clinics. Demand code and infrastructure parity so you are not locked. Store credentials only in your vault.

Vitaly Kovalev

Vitaly Kovalev

Sales Manager

Get a Petersburg Healthcare AI readiness score

Share budget, timeline, stack, and dataset scope. Receive a free readiness audit and cost estimator built for Petersburg and Tri-Cities providers within one business day.

Talk to Experts

Buyer questions

Healthcare AI answers for Petersburg decision makers

Straight responses on cost, timing, data, quality, compliance, and operations. Use these to brief your board or medical executive committee.

What drives the cost of Healthcare AI services in Petersburg VA?

Cost follows scope of workflows, integration depth, and compliance overhead more than model brand names. A single prior-auth assist with read-only EHR access sits far below multi-site coding automation with writebacks. Virginia providers also budget for security reviews, staff training time, and dual environments that keep PHI out of experimental sandboxes. Local market rates for clinical subject-matter experts influence discovery more than cloud compute in early stages.

Data preparation often becomes the silent budget item. If referral packets live as unstructured faxes across Hopewell and Petersburg sites, expect indexing and cleanup hours before any agent shines. Clean FHIR feeds reduce that line. Rubric design for quality scoring adds specialist time but prevents expensive rework after launch. We price that work openly rather than hiding it inside a blurred monthly fee.

Ongoing spend includes model inference, monitoring, and change management when payers alter rules. Token caps and caching keep variable costs predictable for finance. Support retainers cover drift checks and minor prompt edits without opening a new capital project. Compare proposals on three-year operating cost, not just build quotes. Ask every vendor for failures they absorbed on similar scopes so contingencies stay realistic.

How long does it take to build Healthcare AI software for a clinic?

A focused MVP that drafts or triages one workflow usually lands in eight to twelve weeks after data access is real. That window covers discovery, integration stubs, evaluation harnesses, pilot users, and a limited production gate. Full multi-department deployment across Petersburg and satellite locations stretches longer because training, change control, and interface certification must finish without freezing daily care.

Timeline slips almost always trace to delayed credentials or unclear ownership of clinical content. When HIM, compliance, and operations appoint a single decision owner, calendar risk drops. Phaser delivery helps: ship assisted drafting first, then gated automation, then cross-site templates. Each phase produces a go or no-go checkpoint with measured edit rates and cycle times.

Emergency shortcuts that skip gold-set evaluation create longer timelines later when trust collapses. Build the measuring sticks early even if the first interface looks simple. Seasonal surges such as respiratory volume in Southside Virginia should influence pilot timing. We schedule quiet clinic weeks for intense user testing whenever possible. Your estimate will list critical path items explicitly so leadership sees what only the client can unlock.

What data do you need before Healthcare AI implementation starts?

We need a written inventory of systems of record, field definitions, retention rules, and who may grant access. Sample volumes matter: how many referrals per week, how many claims, how many policy documents. De-identified examples of good and bad outcomes seed evaluation sets. Without those anchors, models impress demos and frustrate floor staff later. BAAs and security questionnaires must complete before any PHI leaves your network.

Access patterns beat bulk dumps. Read APIs, secure file drops, or replica databases with row filters reduce risk compared with emailed spreadsheets. Document where shadow systems live, including shared drives that clerical teams trust more than the EHR. Nearby facilities in Colonial Heights often run different templates even under one brand, so site variance belongs in the inventory. Label which content is clinical truth versus outdated intranet pages.

Staff time is data too. SOPs, overtime logs, and denial reason codes quantify the baseline. We also request preferred vocabulary and banned phrases clinicians refuse in patient-facing text. If speech or imaging later enters scope, capture device models and network constraints early. Starting narrow with complete data beats wide scope with partial exports. You will receive a readiness scorecard that marks blockers versus nice-to-haves before contracts lock.

How do you measure quality for custom Healthcare AI outputs?

Quality is defined before coding begins using rubrics tied to business outcomes. For documentation assist we score completeness, factual grounding, and edit distance from clinician finals. For routing tasks we measure precision on urgency labels against a gold set. For revenue tasks we track first-pass yield and denial codes linked to automated steps. Vanity metrics such as raw token volume never guide release decisions.

We reuse evaluation ideas from automated scoring work that applied rubric-based judgments and feedback generation. Each criterion is explicit so two auditors reach the same result. Thresholds determine when an output auto-routes versus waits for a person. Weekly sampling continues after launch because models and prompts drift when source documents change. Dashboards show override reasons so product owners fix root causes.

Clinician champions in Petersburg validate language tone and safety edges that pure engineers miss. Payer-specific rules enter separate test packs when revenue cycle is in play. If scores fall, automation narrows automatically until the cause is repaired. Reports land in language finance and compliance both accept. That discipline keeps quality a managed system rather than a subjective debate after complaints appear.

How do HIPAA compliant AI solutions work for Petersburg providers?

Compliance starts with role boundaries, encryption, audit logs, and legal agreements, not with a model checkbox. PHI stays in controlled stores. Identities flow from your directory. Every retrieval and completion that touches sensitive content writes an immutable event. Business associate agreements cover vendors in the path. Minimum necessary access denies curiosity browsing by engineers and supervisors alike.

Architecture prefers retrieval over training on raw charts whenever possible. Grounded answers cite sources so auditors can reconstruct why a suggestion appeared. Network isolation and private endpoints reduce exposure versus public chat endpoints. Prompt filters and output scanners catch accidental dumps of identifiers. Incident response defines who freezes automated messaging and how patients are notified if required.

Virginia providers still carry state and board obligations beyond HIPAA. We document clinical decision support boundaries so tools never silently act as practicing medicine. Training materials teach staff what the system may draft and what remains human-owned. Security reviews precede production credentials. Continuous monitoring watches anomalous export patterns. This combination lets Petersburg organizations adopt AI without gambling their license or partnership status with larger Richmond systems.

Contact Us

This is what will happen, after you submit form

Need a custom consultation? Ask me!

Plavno has a team of experts ready to start your project. Ask us!

Vitaly Kovalev

Vitaly Kovalev

Sales Manager

Schedule a call

Get in touch

Fill in your details below or find us using these contacts. Let us know how we can help.

No more than 3 files may be attached up to 3MB each.
Formats: doc, docx, pdf, ppt, pptx, xls, xlsx, txt.
Send request