bg image
bg image

Serving Lynchburg & Virginia

Cut clinical admin load before Lynchburg teams hit 2026 capacity walls

Hospital and clinic leaders in Lynchburg lose hours every shift to charts, prior auth, and status calls. That time never returns to the bedside. We build Healthcare AI that removes repetitive work from Virginia care teams without new operational risk. Operators see faster intake, cleaner records, and staff who stay longer on the floor. This is for multi-site clinics, regional systems, and medical groups ready to act this year. Get Healthcare AI cost estimate in 24 hours. Share budget, timeline, stack, and the workflow that breaks first.

Discuss Project

Overview

Why Lynchburg care teams stall on manual work in 2026

Lynchburg health systems and clinics still route too much clinical work through inboxes, spreadsheets, and phone tags. Staff in Forest, Madison Heights, Bedford, and Amherst feel the same pressure when volume rises and headcount does not. Documentation debt grows. Prior authorizations pile up. Nurses leave the floor to chase facts that should already sit in one place. That pattern burns payroll and delays care across Central Virginia. Healthcare AI services fix the bottleneck when they target the real loop, not a demo chatbot. We map intake, chart lookup, status routing, and knowledge retrieval first. Then we ship agents that answer from approved sources, draft routine notes, and push tasks into existing EHRs. Teams keep control of what the model may say and when a human must review. The goal is fewer handoffs and measurable time back on each shift. Trusted Healthcare AI Partner for Lynchburg Businesses. We work with US-based clients, including companies operating in Virginia. Our track record includes 10+ Healthcare AI projects delivered in US market settings, from internal knowledge agents to scoring systems that hold quality at scale. One internal support agent used LLM retrieval and enterprise search so staff could find policy and process answers without pinging a specialist. Another project applied rubric-based evaluation so scoring stayed consistent when volume spiked. Those patterns transfer cleanly to clinical operations where accuracy and audit trails matter. For imaging-heavy workflows we often pair language agents with computer vision so intake and document capture reduce manual entry. Models stay behind your identity controls. Outputs log who asked, what source was used, and whether a clinician signed off. That design keeps compliance teams calm while operations move faster. Leaders in Lynchburg get a clear path from pilot to production without rewriting the entire tech stack. Cost and time pressure will not ease in 2026. Labor is tight across Virginia outpatient and hospital settings. The operators who remove search time, duplicate entry, and night-shift triage noise will protect margins first. We start where the waste is visible, prove value on one line of work, then expand. Scope stays honest. Budget and data quality decide speed more than slideware ever will.

Talk to an Expert
Knowledge retrieval

Knowledge retrieval

Approved corpus answers with citations—no clipboard hunts or specialist pings

Workflow routing

Status & intake routing

Prior auth, referrals, and discharge tasks open in tools you already run

Controlled agents

Human-gated agents

Drafts notes and EHR pushes only with role checks and clinician sign-off

Shift time back

Measurable time back

Fewer handoffs each shift—pilot one line of work, then expand across sites

Clinical stack, not slide decks

Core agent architecture Lynchburg systems actually run

Lynchburg clients receive a production agent layer that sits beside the EHR rather than replacing it. The stack centers on a controlled LLM gateway, a retrieval layer over approved clinical and operational corpuses, and workflow hooks into ticketing, scheduling, and messaging tools. We chose retrieval-augmented answers so staff get citations instead of freeform guesses. That choice came straight from an enterprise employee support agent we shipped where policy lookup had to stay accurate under real load. The same pattern works for protocol search and discharge checklist support in hospital operations.

Request flow is deliberate. A clinician or admin asks a question in a known channel. The gateway checks role and site. Retrieval pulls only from sources that team is allowed to see. The model drafts an answer with source links. High-risk intents route to a human queue before anything posts back to the chart. We implement this with modular services so each hospital site can harden rules without waiting on a full vendor release cycle. Latency targets stay tight because bedside staff will not wait on a chat window that stalls.

Security/compliance is designed in from day one. PHI stays in region. Secrets never sit in prompts. We prefer private model endpoints or customer-owned keys when the risk policy demands it. Access logs feed your SIEM. Prompt and response stores keep retention windows your counsel defines. For multi-entity groups across Virginia we isolate tenant data at the index and storage layers so one clinic never leaks into another. Audit packets ship with every release so privacy reviews do not block go-live for months.

DevOps practice matches regulated delivery. Infrastructure as code defines environments. CI runs evaluation suites that score answer quality against fixed clinical and ops scenarios before promote. Canary traffic starts on a single unit, then expands. Feature flags let us disable a skill without a full rollback. Cost dashboards track token spend per workflow so finance sees the unit economics early. We ground these habits in work already done for internal knowledge agents and automated scoring systems where consistency under volume was the product, not a nice-to-have.

Telephony and form intake plug in when the case needs it. Voice capture becomes structured text. Document packets land in a review queue with confidence flags. Workflow automation closes the loop by creating follow-up tasks only when rules fire. Nothing magic. Clear contracts between intake, reasoner, and action layer. Lynchburg operators keep the systems of record they already paid for while agents remove the swivel-chair work between them.

plavno logo

Build your first
Smart AI project today!

Just tell the Plavno AI Agent about your project - it will ask questions, gather requirements, and propose a tailored solution

What ships

Five Healthcare AI capabilities Lynchburg teams deploy first

Clinical knowledge retrieval agents

Clinical knowledge retrieval agents

Staff waste entire shifts hunting policy PDFs and buried SharePoint pages. A retrieval agent answers from your approved corpus with citations in seconds. We use enterprise search plus LLM synthesis because bare keyword search misses context and bare chatbots invent details. Role filters keep unit-level content scoped. Lynchburg multi-site groups reduce ping traffic to specialists and speed onboarding for new hires who finally find the right answer once.

Workflow automation for care ops

Workflow automation for care ops

Prior auth status, referral packets, and discharge prep still move by email chains across Virginia clinics. Automation agents watch triggers, gather missing fields, and open the next task in the tools you already run. We wire LLM extraction only where documents vary in form. Deterministic rules handle the rest so behavior stays testable. Teams cut cycle time without a risky full EHR rewrite that stalls for a year.

Quality scoring on clinical text

Quality scoring on clinical text

Manual chart audits sample too little and arrive too late. Rubric-based evaluation scores notes and care plans against fixed criteria and drafts richer feedback for reviewers. We used this pattern for scalable assessment in education and middle it to clinical documentation programs. Consistency improves when volume spikes. Managers see where coaching is due instead of relying on sparse spot checks that miss systemic drift.

Secure intake and document capture

Secure intake and document capture

Faxed packets and photo uploads still clog front desks in Lynchburg outpatient settings. Capture pipelines classify pages, extract key fields, and flag low-confidence rows for human review. Models earn their keep when they reduce re-keying, not when they claim to replace clerks. Structured output lands in your registration system through APIs you control. Error rates become measurable instead of anecdotal complaints at the desk.

Staff support copilots for hospitals

Staff support copilots for hospitals

Night shifts lack a full specialist bench. An internal support agent fields routine IT, HR, and protocol questions with retrieval-augmented answers. We built this for enterprise employee support and it transfers to hospital back office and nursing stations. Escalation paths stay visible. Every reply logs sources. Burnout drops when simple questions stop interrupting the few people who still answer pagers at 2 a.m.

Maturity path

From manual charts to guided agents across Virginia sites

A staged path that raises autonomy only after data quality and review gates prove stable for Lynchburg operators.

Clipboard
Team
01

Step 1: Manual baseline map (2 weeks)

We shadow the real workflow on one unit or clinic. Every handoff, system, and failure mode is logged with time stamps. You receive a pain map, risk notes, and a shortlist of automatable steps tied to payroll impact. No model work starts here. Claire scopes stay honest because the evidence is observed, not surveyed. Timeline stays fixed so discovery cannot expand forever.

02

Step 2: Assisted retrieval pilot (3–5 weeks)

We stand up a retrieval agent over a frozen corpus of approved documents. Staff still decide every action. Answers include sources. Evaluation sets measure accuracy against clinician-authored gold answers. You receive dashboards for unused queries and missing content. The pilot proves whether your knowledge base is ready before any write-back to clinical systems happens.

Search in doc
Rocket
03

Step 3: Guarded workflow actions (4–6 weeks)

Selected low-risk actions become agent-triggered under dual control. Examples include drafting status notes or opening ticket follow-ups. Human approval remains mandatory on any patient-facing text. We add cost and latency monitors so finance and ops share the same panel. Rollback flags sit one click away. Deliverables include runbooks and on-call criteria written for your staff.

04

Step 4: Semi-autonomous floors (ongoing)

Only after error budgets hold do we widen autonomy on narrow skills. New sites inherit the same evaluation harness. Drift checks run on schedules. Quarterly reviews retire skills that no longer pay for themselves. You own the model of what remains assisted versus automatic. Expansion across Lynchburg and nearby Virginia sites follows measured gates, not a single big-bang flip.

Case Study

We help customers cut
down on development

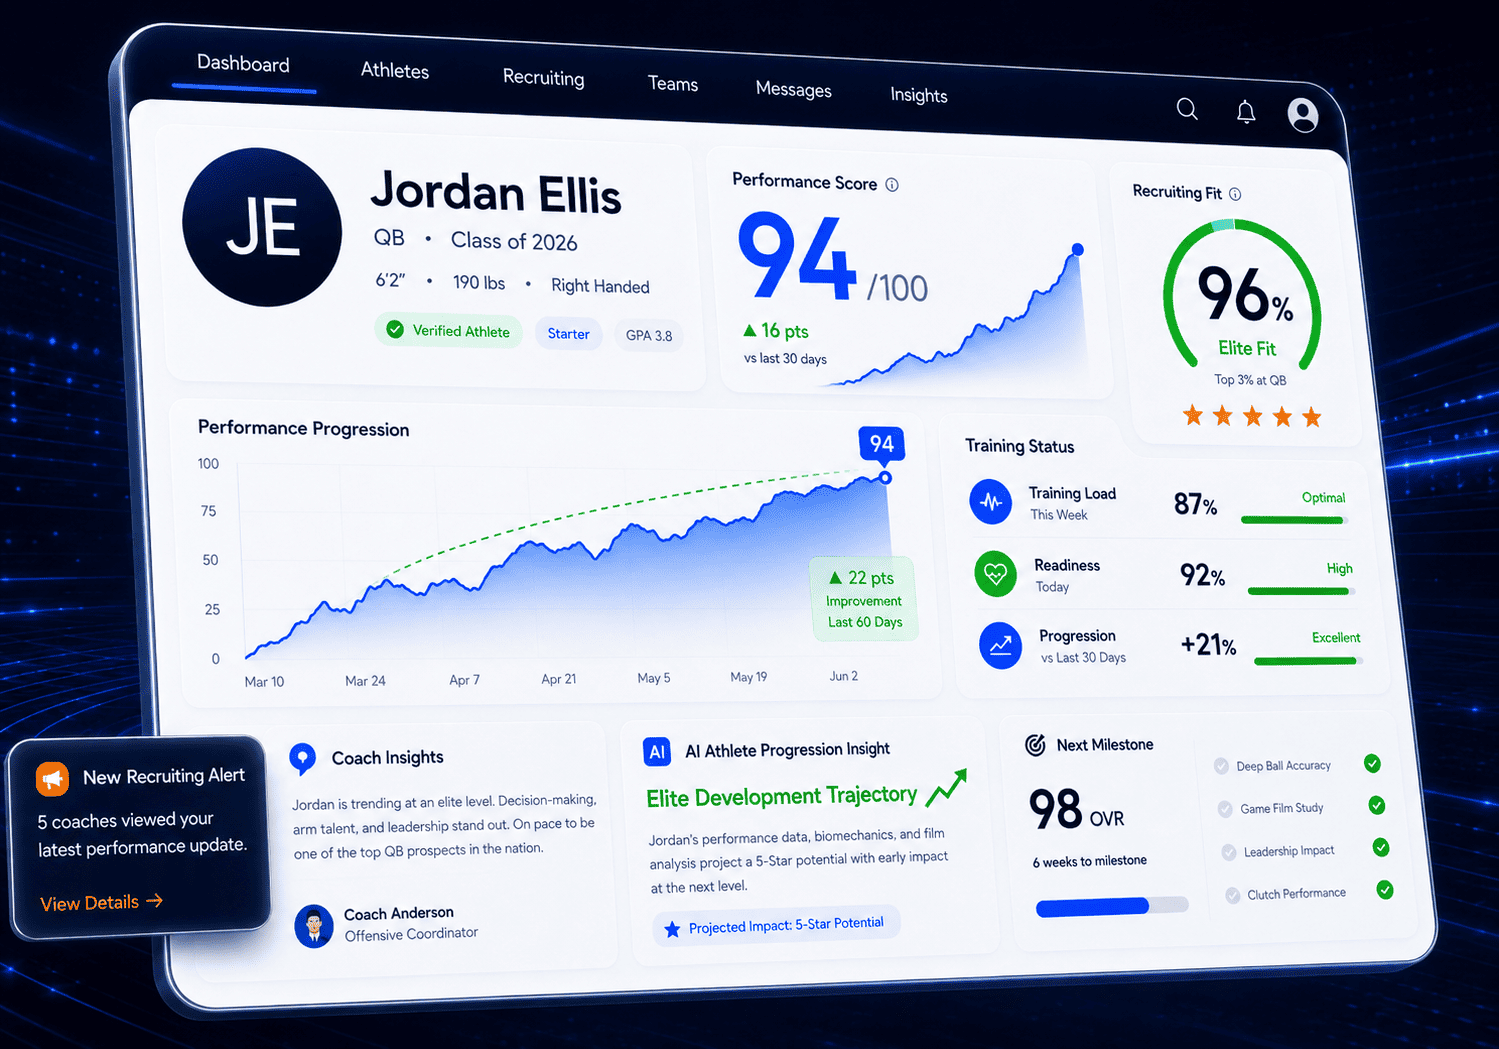
AI-Powered Sports Performance & Recruiting Platform for Virginia Clubs, Academies & Youth Programs

Plavno developed a custom sports technology platform for Virginia-based clubs and academies to combine athlete performance tracking, coach communication, recruiting workflows, and mobile engagement in one ecosystem.

Read More
3x

faster recruiting pipeline

AI-Powered Sports Performance & Recruiting Platform for Virginia Clubs, Academies & Youth Programs

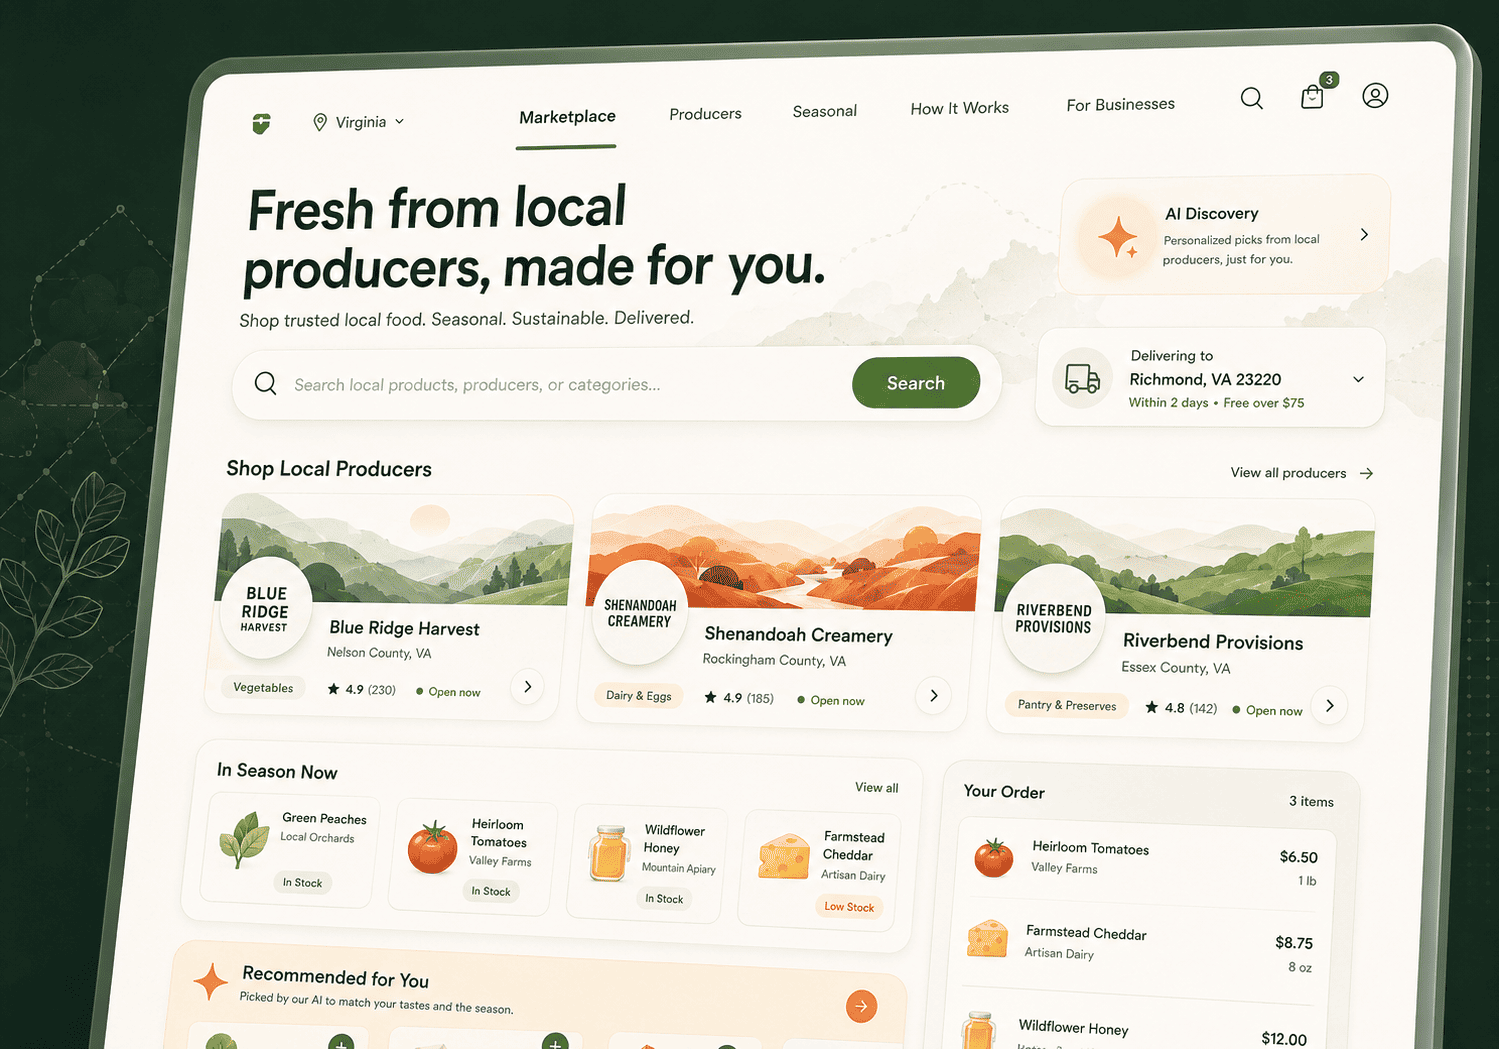
Digital Marketplace for Virginia Farmers, Local Producers & Direct-to-Consumer Food Sales

Plavno developed a custom multi-vendor marketplace for Virginia-based farmers, food producers, and regional sellers to unify product listings, vendor operations, customer ordering, and local fulfillment workflows.

Read More
3x

increase in product discovery relevance

Digital Marketplace for Virginia Farmers, Local Producers & Direct-to-Consumer Food Sales

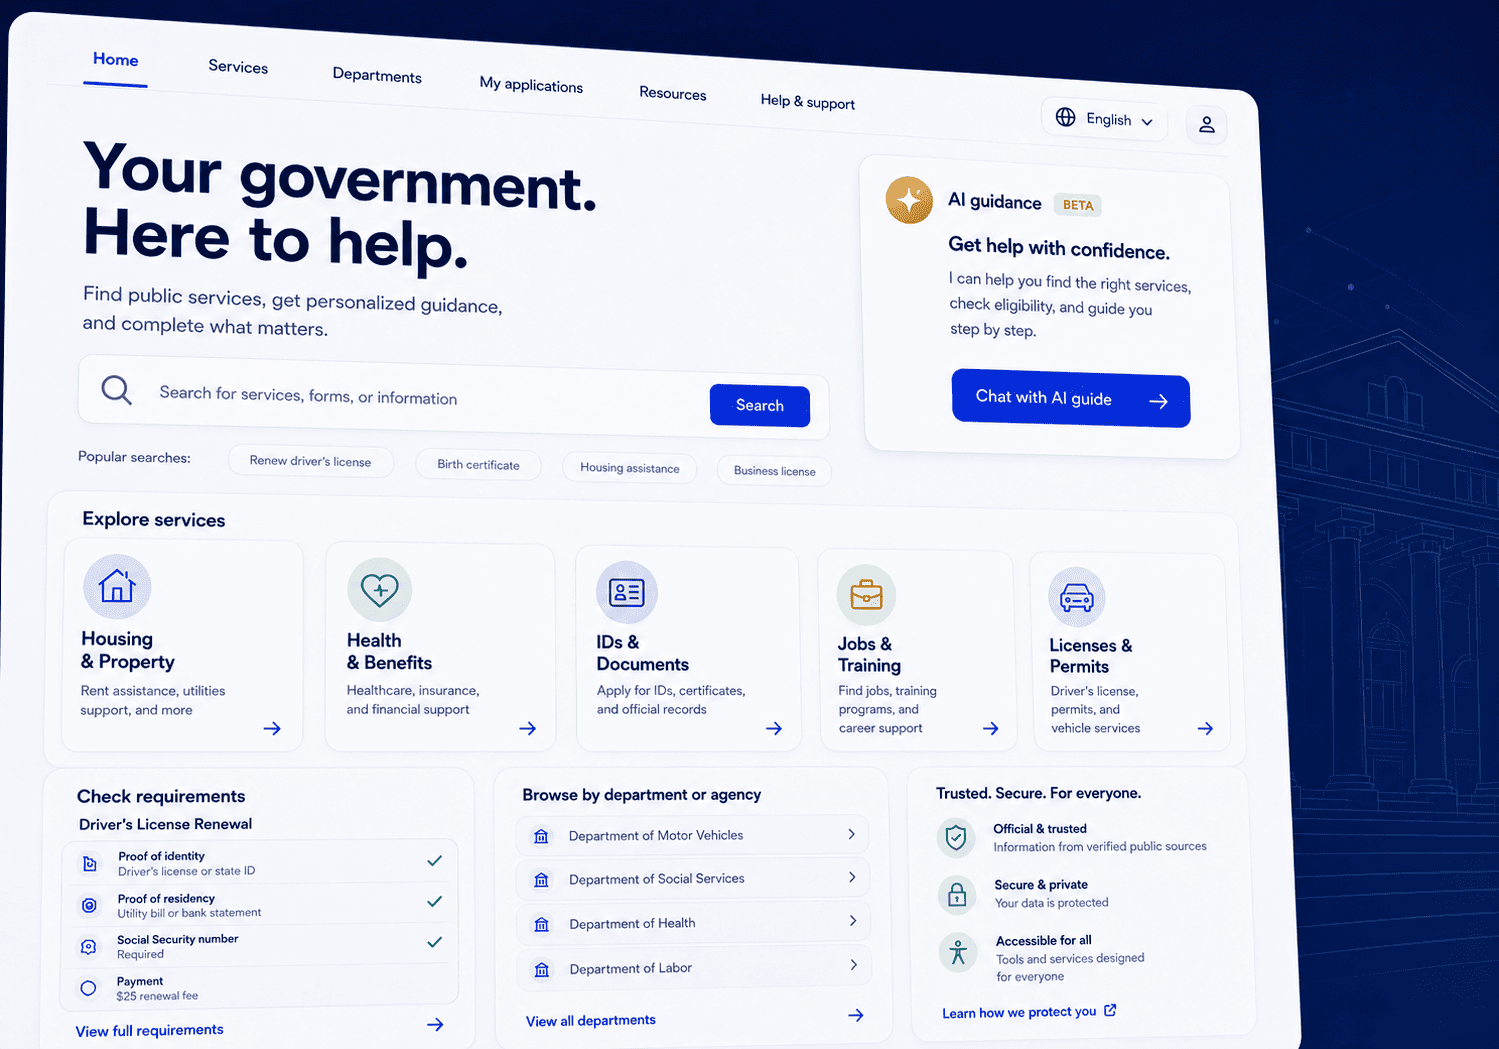
AI-Powered Citizen Services Website Platform for Virginia State Agencies

Plavno developed a modern eGovernment website platform for Virginia state agencies that centralizes citizen services, public information, department content, and an AI-powered guidance agent in one scalable system.

Read More
70%

reduction in routine citizen inquiries to agency staff

AI-Powered Citizen Services Website Platform for Virginia State Agencies

Testimonials

We are trusted by our customers

“They really understand what we need. They’re very professional.”

The 3D configurator has received positive feedback from customers. Moreover, it has generated 30% more business and increased leads significantly, giving the client confidence for the future. Overall, Plavno has led the project seamlessly. Customers can expect a responsible, well-organized partner.

Sergio Artimenia

Commercial Director, RNDpoint

Sergio Artimenia

“We appreciated the impactful contributions of Plavno.”

Plavno's efforts in addressing challenges and implementing effective solutions have played a crucial role in the success of T-Rize. The outcomes achieved have exceeded expectations, revolutionizing the investment sector and ensuring universal access to financial opportunities

Thien Duy Tran

Product Manager, T-Rize Group

Thien Duy Tran

“We are very satisfied with their excellent work”

Through the partnership with Plavno, we built a system used by more than 40 million connected channels. Throughout the engagement, the team was communicative and quick in responding to our concerns. Overall, we were highly satisfied with the results of collaboration.

Michael Bychenok

CEO, MediaCube

Michael Bychenok

“They have a clear understanding of what the end user needs.”

Plavno's codes and designs are user-friendly, and they complete all deliverables within the deadline. They are easy to work with and easily adapt to existing workflows, and the client values their professionalism and expertise. Overall, the team has delivered everything that was promised.

Helen Lonskaya

Head of Growth, Codabrasoft LLC

Helen Lonskaya

“The app was delivered on time without any serious issues.”

The MVP app developed by Plavno is excellent and has all the functionality required. Plavno has delivered on time and ensured a successful execution via regular updates and fast problem-solving. The client is so satisfied with Plavno's work that they'll work with them on developing the full app.

Mitya Smusin

Founder, 24hour.dev

Mitya Smusin

Architecture & Engineering Overview

How Lynchburg Healthcare AI programs hold up after launch

Payroll time returned

Minutes back to bedside

Retrieval and workflow hooks cut hunt time; baselines from live shadowing

Liability gates

Human gate on care text

Models cannot freely write the EHR—logs show who approved every change

Unit cost control

Token cost per workflow

Finance sees spend early so pilot wins never hide unsustainable bills

Honest skill scorecard

Green / yellow / red skills

Edit rates and escalations decide expand, fix, or retire—no vanity KPIs

For Business: Technical ROI & Risk Mitigation

The business case for Healthcare AI in Lynchburg is time returned to billable or bedside work, not flashy demos. Every technical choice should defend payroll, liability, and retention at the same time. Retrieval agents cut the minutes staff burn hunting protocols. Workflow hooks stop packet chase across departments. Quality scoring surfaces chart defects before payers do. Those are the levers bands of regional systems can measure within a quarter.

Risk falls when models cannot freely write into the EHR. We keep a human gate on clinical text that could alter care. Logs show who approved what. That design reduces surprise findings in external audits. Finance also sees token and host spend per workflow so pilot success does not hide an unsustainable bill six months later. Cost control is part of the product, not a later clean-up project.

Competitive risk matters too. Payer rules tighten and documentation standards rise across Virginia. Groups that still rely on heroic night supervisors will lose margin to peers who instrument the same work. Returning even a fraction of admin time per clinician compounds across multi-site networks. Retention improves when nurses stop spending evenings on clerical recovery.

We refuse vanity metrics. Baselines come from the discovery shadowing. After launch we track minutes saved per task class, escalations per hundred queries, and reviewer edit rates. If a skill fails those tests it is retired. That discipline protects capital and keeps the program honest with clinical leadership.

Leaders get a board-ready view. Color is simple. Green skills expand. Yellow skills need content or prompt work. Red skills pause. No hubris about full autonomy in a regulated setting. The ROI story stays tied to operations you already staff and fund.

1

Decision record & freeze

Replaceable model endpoints behind stable tools—one workflow family, read/write rights locked with EHR

2

Gates: corpus · policy · write

Each gate has an owner and stop condition; threat notes document private vs shared endpoint trade-offs

3

CI governance & canaries

Prompt/tool updates ride code path; evals block accuracy drops; kill switches and clinical liaison on-call

4

Content ops + clean exit

Hit-rate monitoring, idle skills cut; indexes, prompts, and eval data always exportable

For CTOs: Architecture & Technical Lifecycle

Lifecycle starts with a written decision record, not a model bake-off. Architecture favors replaceable model endpoints behind a stable tool and policy layer. That lets you swap providers when price or capability shifts without rewriting every skill. Kickoff freezes scope to one workflow family and one data domain. Integration contracts define read versus write rights up front with your EHR and identity teams.

Decision points arrive at corpus freeze, policy approval, and first write path. Each gate has an owner and a stop condition. Trade-offs are explicit. Hosted private endpoints cost more and cut egress risk. Shared endpoints move faster and need stricter redaction. We document the choice with threat notes so security does not reverse it after build cost is sunk.

Governance runs through change tickets like any other production service. Prompt and tool updates ride the same CI path as code. Evaluation sets block merges that drop accuracy or raise toxicity on clinical scenarios. Production has canaries and kill switches. On-call includes clinical liaison paths for content errors, not only uptime pages.

Post-launch, lifecycle becomes content ops plus model ops. Knowledge owners refresh source packs on a calendar. Engineers watch retrieval hit rates and fallback frequency. Product leads review which skills fire and which sit idle. Idle skills get cut to protect spend. This is how an enterprise search and RAG agent stayed useful after launch instead of rotting as a unused sidebar.

Exit options stay open. All indexes, prompts, and evaluation data export. You are not trapped if strategy changes. That matters for Virginia systems that may join larger networks and need clean technology accounts later.

Retrieval layer

Retrieval layer

PDF/DOCX/HTML loaders → chunked metadata → hybrid dense + keyword search on clinical codes

Reasoning runtime

Reasoning + typed tools

search_policy, open_ticket, fetch_slot—policy engine allows or denies by role and patient context

Scoring loop

Rubric scoring loop

Structured criteria + few-shot; reviewer corrections feed eval sets, never silent prompt edits

Fail-closed edges

Action layer & CI edges

Empty retrieval, PHI redaction, clock skew—Python orchestration, queues, flags, vault secrets

For Engineers: Implementation Details & Stack

Implementation is boring on purpose. We separate retrieval, reasoning, and action so each layer can fail closed. Document loaders normalize PDF, DOCX, and HTML into chunked text with metadata for site, role, and effective date. Embeddings land in a vector store you host or we host under your key policy. Hybrid search mixes dense vectors with keyword filters because clinical codes and proper nouns still need exact matches.

The agent runtime exposes tools as typed functions. Examples include search_policy, open_ticket, and fetch_appointment_slot. The model proposes a tool call. A policy engine allows or denies it based on role and patient context presence. We learned this split on internal knowledge assistants where free tool use caused noisy side effects. Healthcare needs the same discipline with sharper teeth.

For scoring flows we encode rubrics as structured criteria and few-shot exemplars. The model returns machine-readable fields plus rationales. Human reviewers correct edges. Corrections feed the evaluation set, not silent prompt edits. That loop came from building automated graders that had to stay consistent when volume climbed. Apply it to note quality or referral completeness and measure the same way.

Edge cases get tests. Empty retrieval. Conflicting sources. PHI appearing in a free-text field that should be redacted. Clock skew on appointments. We run these in CI with fixtures, not only happy path demos. Observability hooks emit spans for retrieval latency, token counts, and tool error rates. Engineers debug from traces instead of screenshots from angry charge nurses.

Stack choices stay pragmatic. Python services for orchestration. Type-safe APIs at the edges. Message queues when intake spikes. Feature flags for skill rollout. Secrets in a managed vault. Nothing exotic unless a constraint forces it. Production truth beats conference novelty every time on a hospital floor.

HIPAA controls

HIPAA-aligned controls

PHI env segregation, SSO + MFA, least-privilege scopes, logged break-glass paths

Quality observability

Ops-grade observability

Empty rates, overrides, token cost/task, p95 latency—shared with clinical ops live

Multi-site deploy

Canary multi-site deploy

IaC promotion gates across Virginia instances; blue-green cuts freeze risk on clinic days

Threat & cost guardrails

Threat models & throttles

Prompt injection / exfil red-teams in evals; budgets auto-throttle idle high-spend skills

Infrastructure, Observability & Security

US healthcare clients demand provable controls. We design for HIPAA-aligned controls, least privilege, and full auditability before the first pilot user lands. Environments segregate PHI from analytics pads. Encryption covers data at rest and in transit. Identity integrates with your SSO and enforces MFA. Service accounts hold only the scopes a given skill needs. Break-glass paths are logged and time-boxed.

Observability covers more than uptime. We monitor retrieval empty rates, answer refusal rates, human override frequency, token cost per successful task, and p95 latency by skill. Alerts fire when quality drifts or spend spikes. Dashboards are shared with clinical ops so trust is continuous, not a quarterly slide. Incident response runbooks include content purge steps if a bad source enters the index.

Deployment for multi-site Virginia groups uses environment per stage with promotion gates. Blue-green or canary layouts reduce freeze risk on busy clinic days. Infrastructure as code keeps drift low across Forest and Bedford instances that once would have been hand-built snowflakes. Backups and restore drills are scheduled, not assumed.

Security reviews receive threat models for prompt injection, data exfiltration via tools, and over-broad retrieval. Red-team cases live in the eval suite. Vendor BAAs and subprocessors are listed before contract signature. We do not improvise compliance after a sales demo goes well. That posture came from shipping enterprise agents where legal review was part of the critical path, not an afterthought.

Post-launch cost control uses budgets and automatic throttles per department. Skills that burn tokens without outcomes lose priority. Quarterly resilience tests rehearse key revocation and model endpoint failover. The goal is a system your CISO can defend and your CFO can fund without drama.

Choose with eyes open

Why Lynchburg teams pick deep engineering over generic AI shops

Side-by-side differences that matter when clinical risk, audit trails, and unit economics decide the winner.

Generic Agencies
Our Platform (Deep Engineering Expertise)
Retrieval with source citations on every clinical answer
checkmark
Human approval gates on patient-facing outputs
checkmark
Evaluation suites blocking low-quality releases
checkmark
Token and workflow cost dashboards from week one
checkmark
Slide-only strategy workshops without production code
checkmark
HIPAA-aligned logging, SSO, and tenant isolation
checkmark
Skills retired when idle or failing error budgets
checkmark

Data paths that survive audit

Integration fabric that keeps Virginia EHRs in charge

The second build concern is not model brand. It is how cleanly Healthcare AI attaches to the systems Lynchburg already runs. We treat the EHR, identity provider, ticket system, and document stores as sources of truth. Agents read through approved APIs and write only where contracts allow. That stance prevents shadow databases that become toxic when auditors arrive. Integration maps list every field, rate limit, and failure mode before code lands.

Data quality gates sit in front of any model call. Missing MRNs, stale allergies, or conflicting statuses freeze the flow and open a human task. We learned to respect dirty inputs while building enterprise retrieval agents where incomplete documents produced confident nonsense. Healthcare has less tolerance for that failure mode. Validation schemas catch shape errors early. Sampling jobs measure field completeness over time so leadership sees whether upstream cleanup is working.

Interface design prefers event-driven hooks when the vendor platform offers them. Nightly batch remains only when real-time feeds are impossible. De-identification layers strip or hash identifiers for lower environments so engineers never train against raw production PHI. Where computer-assisted coding or imaging metadata enters the path, those payloads stay versioned and reversible. Finance then knows exactly which integration line item drives cost.

Security/compliance reviews own the interface catalog. Each connection has an owner, a BAA reference if needed, and a revocation plan. Secrets rotate on a schedule. We document breakers that stop outbound calls if anomaly scores rise. That is how multi-site programs across Altavista and Amherst stay manageable rather than becoming a hollow center of point scripts. Least privilege is enforced in IAM groups mirrored from job roles, not in a shared service account that everyone quietly reuses.

Change management ends the build story. Interface consumers get contract tests. A failing EHR sandox build blocks promote. Clinical content owners approve new source packs the same way code owners approve pull requests. This fabric is what lets custom medical AI integration in Lynchburg scale past a single clinic pilot without rewriting the house. Models can change. The pipes and policies should not have to.

Eugene Katovich

Eugene Katovich

Sales Manager

Need a custom software solution? We’re ready to help!

Plavno has a team of skilled developers ready to tackle the project. Ask me!

Get a Free Quote

Before you buy

Vendor readiness checks for Lynchburg Healthcare AI buys in 2026

  • Freeze the target workflow in writing — Name the unit, the users, and the systems of record. List the steps that consume measured minutes today. Exclude moonshot voice bots if the real bleed is packet chase. Require the vendor to restate this scope back to you before any proposal lands. Ambiguity here is how pilots drift into chat demos nobody will fund later. Attach baseline time studies from at least one week of observation. Confirm who signs clinical acceptance when quality holds.

  • Demand a retrieval and citation plan — Ask where documents live, who owns them, and how often they refresh. Reject pure parametric answers for protocol questions. Require sample answers that show sources. Confirm role filters so one clinic cannot see another clinic’s content. Verify that empty retrieval fails closed instead of inventing text. Document retention rules for logs that may contain PHI. Get the purge process in writing before go-live talks begin.

  • Inspect human-in-the-loop controls — Map every agent action that could send patient-facing language. Place an approval step with named roles. Measure override rates after week two. If overrides stay high, the skill is not ready for wider rollout. Require an audit trail that survives legal preservation holds. Confirm mobile and desktop paths both enforce the same gate. Train the supervisors who will actually click approve at 7 a.m.

  • Price the full run rate, not the pilot waiver — Include model tokens, hosting, monitoring, and content ops hours. Ask for unit costs per hundred successful tasks. Reject unlimited pilot discounts that rename as surprise invoices. Cap monthly spend with hard throttle alerts. Compare that number to overtime hours the workflow currently burns. Finance and clinical ops should sign the same sheet. Update the model when volumes change after expansion.

  • Score post-launch operations maturity — Request runbooks, on-call rotations, and drift evaluation schedules. Ask what was retired on prior projects when a skill failed. Confirm you can export indexes, prompts, and metrics if you change vendors. Verify SSL, SSO, and logging meet hospital policy without exceptions. Schedule a tabletop incident drill before publicity. Keep scores in a shared checklist so comparisons between bids stay objective.

Vitaly Kovalev

Vitaly Kovalev

Sales Manager

Get a Lynchburg Healthcare AI readiness audit

Share budget, timeline, stack, and dataset scope. Receive a scored readiness audit and cost estimator built for Lynchburg and Central Virginia care operators.

Talk to Experts

Straight answers

Healthcare AI questions from Lynchburg and Virginia buyers

Practical detail on cost, timing, data, quality, security, and post-launch care for regional health teams.

What drives the cost of Healthcare AI services for Lynchburg organizations?

Cost tracks scope, data readiness, and integration depth more than which model logo appears on a slide. A single retrieval agent over a clean policy library costs far less than multi-site write-backs into an EHR with complex consent rules. Local market wages for clinical subject matter time also matter because every serious pilot needs reviewers from your own staff. Cloud spend follows token volume and whether you require private endpoints inside a tighter security boundary. Lynchburg groups should budget discovery, corpus cleanup, pilot build, evaluation, and three months of hypercare as separate lines. Skipping cleanup looks cheaper and fails in week two when answers cite outdated PDFs. Integration to identity and ticketing is usually moderate. Direct EHR write paths raise both engineering hours and compliance review time. Those reviews are healthy. They also extend wall-clock schedules and invoices. We price after seeing stack diagrams, sample documents, and target workflows. Two clinics with the same headcount can diverge by a wide margin if one has structured APIs and the other lives on fax. Ask every vendor for unit economics per successful task so finance can model growth. Avoid unlimited seat promises that hide token burn. Demand alerts before monthly caps breach. Regional dynamics matter. Travel for onsite shadowing across Forest or Bedford is minor compared to rework from remote-only discovery that missed real hall traffic patterns. If your legal team needs fresh BAAs with model hosts, add calendar time and counsel cost. The honest answer is a range tied to evidence, not a single number from a marketing package. Bring budget, timeline, and dataset notes to the first call so estimates stay real.

How long does it take to build Healthcare AI software for a clinic or hospital?

Timelines split into MVP and full deployment, and they should. A focused MVP that answers operational questions from an approved corpus can reach limited users in roughly six to ten weeks when data is available and stakeholders meet weekly. That MVP still includes evaluation sets, role-based access, and logging. Anything faster usually skips the parts that stop clinical risk. Full deployment across multiple Virginia sites with workflow write actions commonly runs four to seven months depending on EHR interfaces and change boards. MVP goals stay narrow. One unit. One skill family. No broad autonomy. Success criteria are written before build starts, such as answer accuracy on a frozen test pack and median response time under an agreed threshold. Staff train on how to escalate wrong answers. Product stops when criteria hold, not when a calendar page turns. This discipline came from shipping internal knowledge agents where a wide launch without proof created noise instead of value. Full deployment adds interface certification, security review, content ownership, and multi-site config. Scheduling with hospital IT freezes can dominate the calendar more than code. Build buffers for those gates. Parallel work helps. While security reviews run, you can expand evaluation cases and draft runbooks. While content owners clean sources, engineers harden monitoring. Seasonal load also shapes plans. Avoid go-live in peak flu windows if the target unit is already stretched. Prefer quieter weeks for cutover with steroids of support staff on shift. After launch, plan a freeze for model and prompt changes during the first stabilization month so signal is clean. MUST timelines that ignore these realities fail quietly. Honest schedules include them from the first estimate.

What data do you need before a Healthcare AI implementation starts?

Start with process truths, not just files. We need a written map of the workflow, named systems, and the users who will touch the agent. Then come document packs with owners and effective dates. Policy manuals, order sets, onboarding guides, and FAQ dumps are common starters when the goal is staff support or protocol retrieval. Structured extracts from ticketing or EHR read views help when the goal is status automation. Sample tickets with outcomes let us build evaluation cases that match real work. Quality beats volume. Fifty clean, current protocols outperform five thousand outdated PDFs with mixed access rights. We ask for sensitivity labels so PHI is handled correctly from day one. If you cannot yet de-identify training materials, lower environments stay off full content and tests use synthetic analogs. Identity group lists and role definitions belong in the initial packet because retrieval filters depend on them. Integration assets reduce later thrash. API docs, sandbox credentials, rate limits, and prior incident notes about the interface save weeks. Where fax or email remain critical paths, provide volume counts and example packets. That evidence guides capture design instead of guesswork. Analytics exports showing where time currently burns help codify ROI baselines. Legal agreements sit beside the data. BAAs, data processing terms, and retention rules should be ready before corpora move. If counsel has banned certain model hosts, say so early so architecture does not need a late pivot. Lynchburg teams that prepare this pack shorten discovery and cut change orders. Incomplete packs do not stop us, but they do shift the first weeks into scavenger work rather than building value.

How do you evaluate quality and measure Healthcare AI performance?

Quality is measured against fixed scenarios that clinicians and ops leads write with us. Each scenario has an expected answer shape, required sources, and a severity rating if wrong. Automated runs score retrieval hit rate, faithfulness to sources, and schema validity of any structured output. Human reviewers spot-check edges the harness cannot yet judge. Scores gate promotion the same way unit tests gate code. Vanity chat demos never substitute for this pack. Operational metrics sit next to model metrics. We track median and p95 latency, escalation rate, human edit distance on drafts, and successful task completion. Cost per successful task keeps finance aligned with clinical wins. When we applied rubric-based evaluation on large assessment loads in education, consistency under volume was the product. Clinical documentation and referral completeness scoring inherit the same idea with stricter privacy controls. Drift detection runs on a schedule after launch. New document versions can silently change answer quality if nobody rechecks. Fresh evaluation cases catch that. Overrides from staff feed a backlog of failures that engenders new tests. Skills that fail error budgets pause automatically. This is evaluations as product operations, not a pre-sales show. Reporting is shared. Clinical sponsors see quality and safety views. Engineering sees latency and error traces. Finance sees spend. When the three views disagree, we stop expansion until they align. That habit prevents glossy pilots that collapse under real Lynchburg shift pressure. Measurement starts in week one of discovery when baselines are captured from shadowing, not after launch when memory fades.

How do you handle compliance, security, and HIPAA concerns for Healthcare AI?

Compliance starts with data flow diagrams and threat models before write access exists. PHI is classified. Lower environments avoid it when possible. Production access uses SSO, MFA, and least-privilege roles mapped to job functions. Encryption covers storage and transit. Audit logs capture prompts, retrieved sources, outputs, and approver identity for actions that touch patients. Retention matches your legal schedule, not an engineer convenience default. Vendor and model choices respect BAAs and regional hosting needs. Some clients require private endpoints and customer-managed keys. Others accept stronger hosted options with clear subprocessors. We document the decision and the residual risk so security leadership can accept or reject with eyes open. Prompt injection and tool abuse cases live in the security test pack. Failures block release. Operational controls matter as much as network controls. Human approval gates remain on patient-facing text. Break-glass admin paths are time-bound and reviewed. Incident runbooks cover mistaken disclosure, bad source publication, and model endpoint failover. Tabletop drills before go-live shake out ownership gaps. Security questionnaires from Virginia hospital groups are answered with evidence packs, not marketing prose. We do not claim a rubber stamp that replaces your counsel. We implement engineering patterns that make their review faster and cleaner. Tenant isolation for multi-entity groups prevents cross-clinic retrieval. Content owners must approve source packs. Changes ride through change control. That posture holds when auditors arrive and when a partner hospital joins the network mid-year.

Contact Us

This is what will happen, after you submit form

Need a custom consultation? Ask me!

Plavno has a team of experts ready to start your project. Ask us!

Vitaly Kovalev

Vitaly Kovalev

Sales Manager

Schedule a call

Get in touch

Fill in your details below or find us using these contacts. Let us know how we can help.

No more than 3 files may be attached up to 3MB each.
Formats: doc, docx, pdf, ppt, pptx, xls, xlsx, txt.
Send request