bg image
bg image

Serving Hampton & Virginia

Cut chart burden and claim delays for Hampton care teams in 2026

Hampton health systems still burn hours on charts, referrals, and prior auth. That cost shows up in overtime, backlog, and staff turnover. We build Healthcare AI that takes repeat work off clinicians and revenue staff. You keep judgment where it matters. Ops join cleanly with the tools you already run. Built for hospitals, specialty groups, and payers across Hampton Roads. Get Healthcare AI cost estimate in 24 hours.

Discuss Project

Overview

Why Hampton care groups need AI that ships

Hampton sits inside a dense care corridor. Langley-linked clinics, Sentara-serving practices, and shipyard contractors all feed the same hospitals. Chart volume rises faster than hiring. Nights stretch. Referral loops stall. Leaders need tools that cut drudge work without adding risk. That is the job of focused medical AI, not another slide deck. Trusted Healthcare AI Partner for Hampton Businesses. We work with US-based clients, including companies operating in Virginia. Our teams ship models that read notes, route cases, and answer staff questions against approved knowledge. The same retrieval pattern we used for an enterprise internal support agent applies when clinicians ask policy or protocol questions. Answers stay grounded in your sources, not free-form guesses. Local groups from Newport News to Norfolk and Virginia Beach share one constraint. Systems must respect HIPAA and sit beside EHR and claims stacks that cannot go offline. Quiet computer vision and document AI can pull structured fields from forms and imaging packets. Recall beats showy demos. Failure modes matter more than peak accuracy in a lab. We treat every pilot as a production path. Scope the workflow, map PHI flows, then lock evaluation before anyone touches live patients. Ten-plus AI programs delivered in the US market taught us where projects stall. Data access, owner clarity, and audit trails decide speed more than model brand. Hampton buyers get a plan they can defend to compliance and finance. Outcomes show up as fewer after-hours notes, faster prior auth packets, and cleaner handoffs between clinics in Portsmouth and the Peninsula. Staff keep control. The system drafts, flags, and files under policy. That is how custom Healthcare AI earns a budget line in 2026.

Talk to an Expert
Clinical note AI

Clinical note AI

Drafts grounded in transcripts and prior notes under retrieval control

Case routing

Case & prior auth routing

Assemble criteria, flag missing labs, speed packets for Peninsula groups

Staff knowledge agents

Staff knowledge agents

Policy answers from approved sources only — no free-form guesses

HIPAA-bound document AI

HIPAA-bound document AI

Vision & form extract beside EHR/claims with audit-ready PHI maps

Production stack, not demos

Architecture that keeps PHI in bounds

Hampton buyers do not need another chatbot chassis. They need services that sit next to EHR events, claims queues, and staff knowledge bases. We design event-driven pipelines with clear trust boundaries. Identifiers stay tokenized where policy allows. Model calls run in VPC or private endpoints. Every prompt and response that touches care data lands in an immutable log for audit. Core pieces follow work we already shipped. Retrieval-augmented answers backed by enterprise search keep staff agents honest, the same pattern used in our internal knowledge assistant. Workflow automation wraps the model so a draft note, coding suggestion, or denial packet cannot leave review gates. For scoring-style tasks we apply rubric-driven evaluation similar to the AI grader we built for EdTech, so quality rules stay explicit and editable. Security/compliance is not a bolt-on. Role maps mirror your IAM. Secrets live in managed vaults. Encryption covers rest and transit. We document BAAs, data retention, and purge paths before first PHI lands in a non-prod store. Red team prompts and synthetic patients exercise edges before go-live. Access reviews are products, not slides. DevOps means blue-green or canary releases for inference services, feature flags for workflow steps, and cost caps on token spend. Observability covers latency, refusal rates, retrieval hit rates, and human override rates. Alerts route to on-call with runbooks. Model and prompt versions pin to compliance packets so a rollback is a config change, not a mystery. Integration uses HL7 FHIR where the host allows it, plus secure file drops and message buses for older stacks. We refuse silent overwrites of clinical fields. Humans confirm on high-risk paths. For imaging or scanned packets, document and vision models extract fields into structured forms that revenue and nursing teams already know. Metric gates block promotion when drift or error budgets break. That keeps enterprise Healthcare AI from becoming shelfware after the pilot party ends.

plavno logo

Build your first
Smart AI project today!

Just tell the Plavno AI Agent about your project - it will ask questions, gather requirements, and propose a tailored solution

From ambient risk to live traffic

How Hampton teams reach a safe first release

A four-phase path that starts with PHI maps and ends with monitored production traffic under your change board.

Clipboard
Team
01

Step 1: Workflow and PHI discovery (2 weeks)

We shadow the real process in clinic or billing. Owners name systems of record, data classes, and failure cost. You receive a risk map, success metrics, and a go or no-go gate. No model training starts until legal and security clear the scope. Timeline stays fixed at two weeks unless sites block access.

02

Step 2: Data contracts and gold sets (2–3 weeks)

Engineers define schemas, retention, and de-id rules. Clinicians label a gold set that matches the exact task. Evaluation scripts score drafts against that set before any live path opens. You get sample outputs, scorecards, and a written residual-risk list. Gaps surface early while budgets still flex.

Search in doc
Rocket
03

Step 3: Contained pilot (3–4 weeks)

The service runs on limited users with dual control and full logging. We tune prompts, retrieval, and handoff UX against real tickets. Weekly reviews track time saved and override reasons. Exit criteria are written in advance so the pilot cannot drift. Mid-course fixes stay inside the same sprint cadence.

04

Step 4: Production hardening (2–3 weeks)

We finish SSO, audit export, cost budgets, and on-call runbooks. Change tickets route through your CAB. Training materials and admin guides ship with the cutover plan. Post-launch reviews land at 14 and 45 days with error budgets visible. Ownership of the backlog returns to your product lead with our optional retainer.

What ships in the first year

Capabilities Hampton operators actually fund

Clinical note assistance

Clinical note assistance

Providers in Hampton lose evenings to chart cleanup. Ambient or after-visit drafts cut that drag without replacing judgment. We ground drafts in visit transcripts and prior notes under retrieval control. Structured sections match your template library. Overrides train the next iteration. Outputs stay in the EHR draft state until sign-off.

Prior auth packet builders

Prior auth packet builders

Specialty groups near Newport News wait days on incomplete packets. Agents assemble criteria, attach evidence, and flag missing labs. Staff review once instead of hunting charts. Rules sit in versioned configs your medical director owns. Submit paths still use the portal or fax bridge you require today.

Staff knowledge agents

Staff knowledge agents

New nurses and billers ask the same policy questions each week. An internal agent answers from approved manuals with citations. That mirrors our enterprise employee support agent with retrieval-augmented answers and workflow hooks. Hallucination risk drops because the system refuses when sources are thin. Analytics show which pages need rewrite.

Coding and charge review

Coding and charge review

Missed charges and denials erode margin for clinics across Chesapeake. Models propose codes against notes and order sets with rule checks. Coders accept, edit, or reject in bulk. Rubric scoring keeps quality visible the way our AI grader enforced consistent feedback. Finance sees clean before and after denial rates.

Document and form intake

Document and form intake

Fax and portal PDFs still choke Peninsula front desks. Vision and document models extract fields into your work queues. Confidence scores route low-confidence rows to humans first. Validation rules match payer and program rules you supply. Cycle time falls without buying a full OCR platform rebuild.

Case Study

We help customers cut
down on development

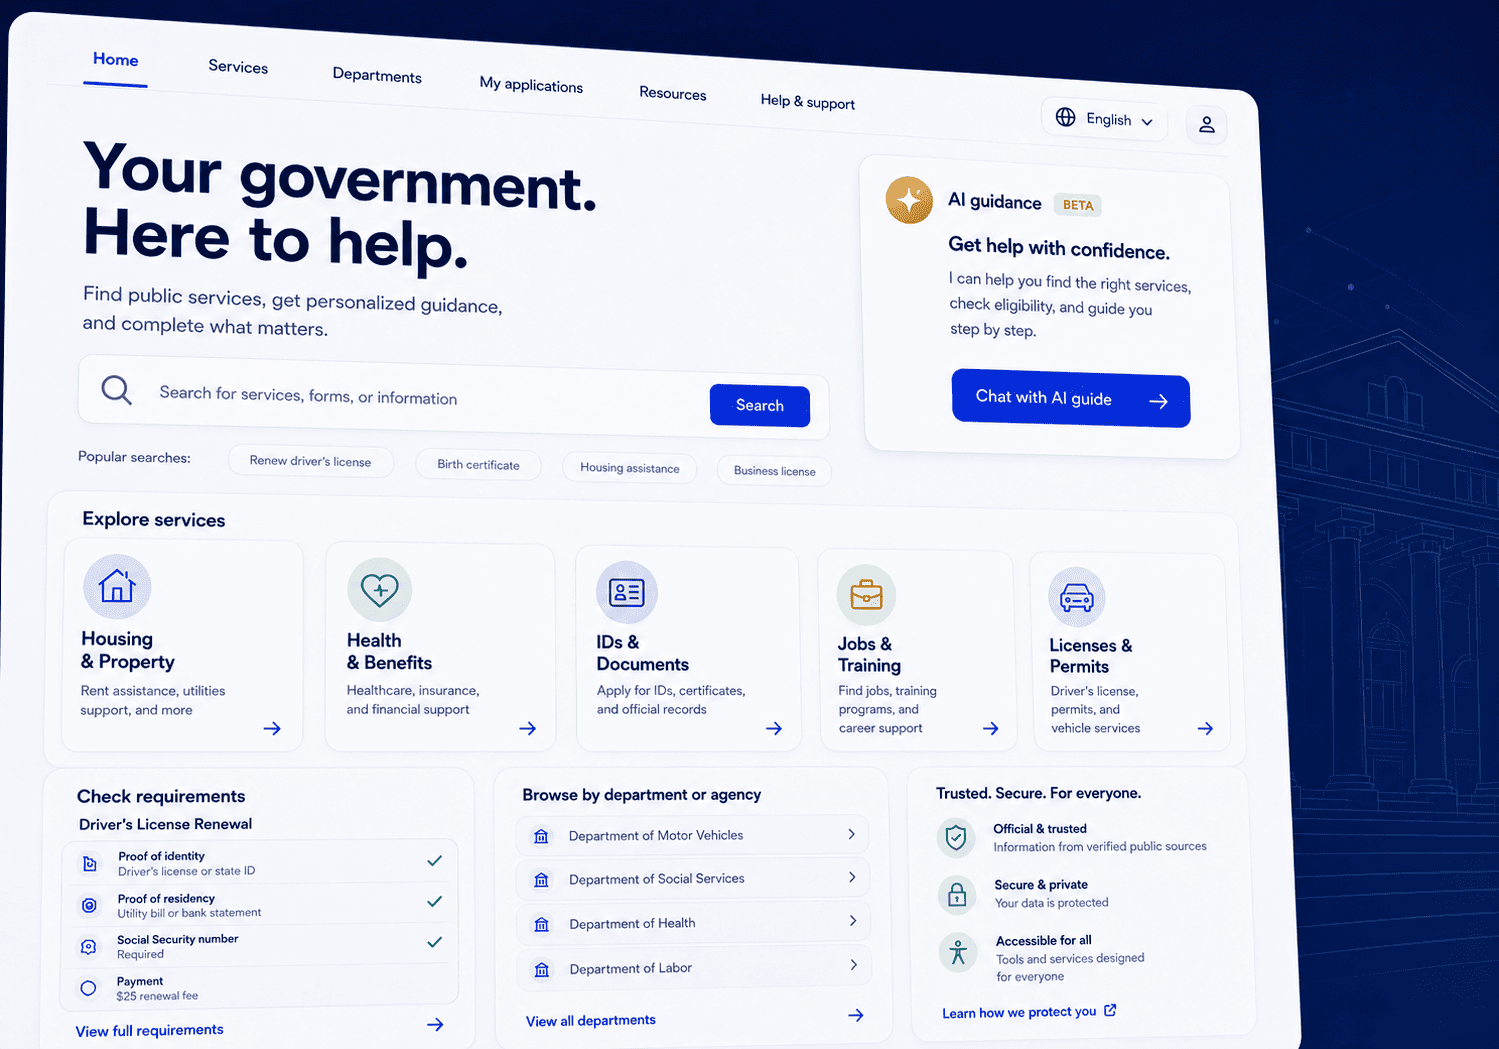
AI-Powered Citizen Services Website Platform for Virginia State Agencies

Plavno developed a modern eGovernment website platform for Virginia state agencies that centralizes citizen services, public information, department content, and an AI-powered guidance agent in one scalable system.

Read More
70%

reduction in routine citizen inquiries to agency staff

AI-Powered Citizen Services Website Platform for Virginia State Agencies

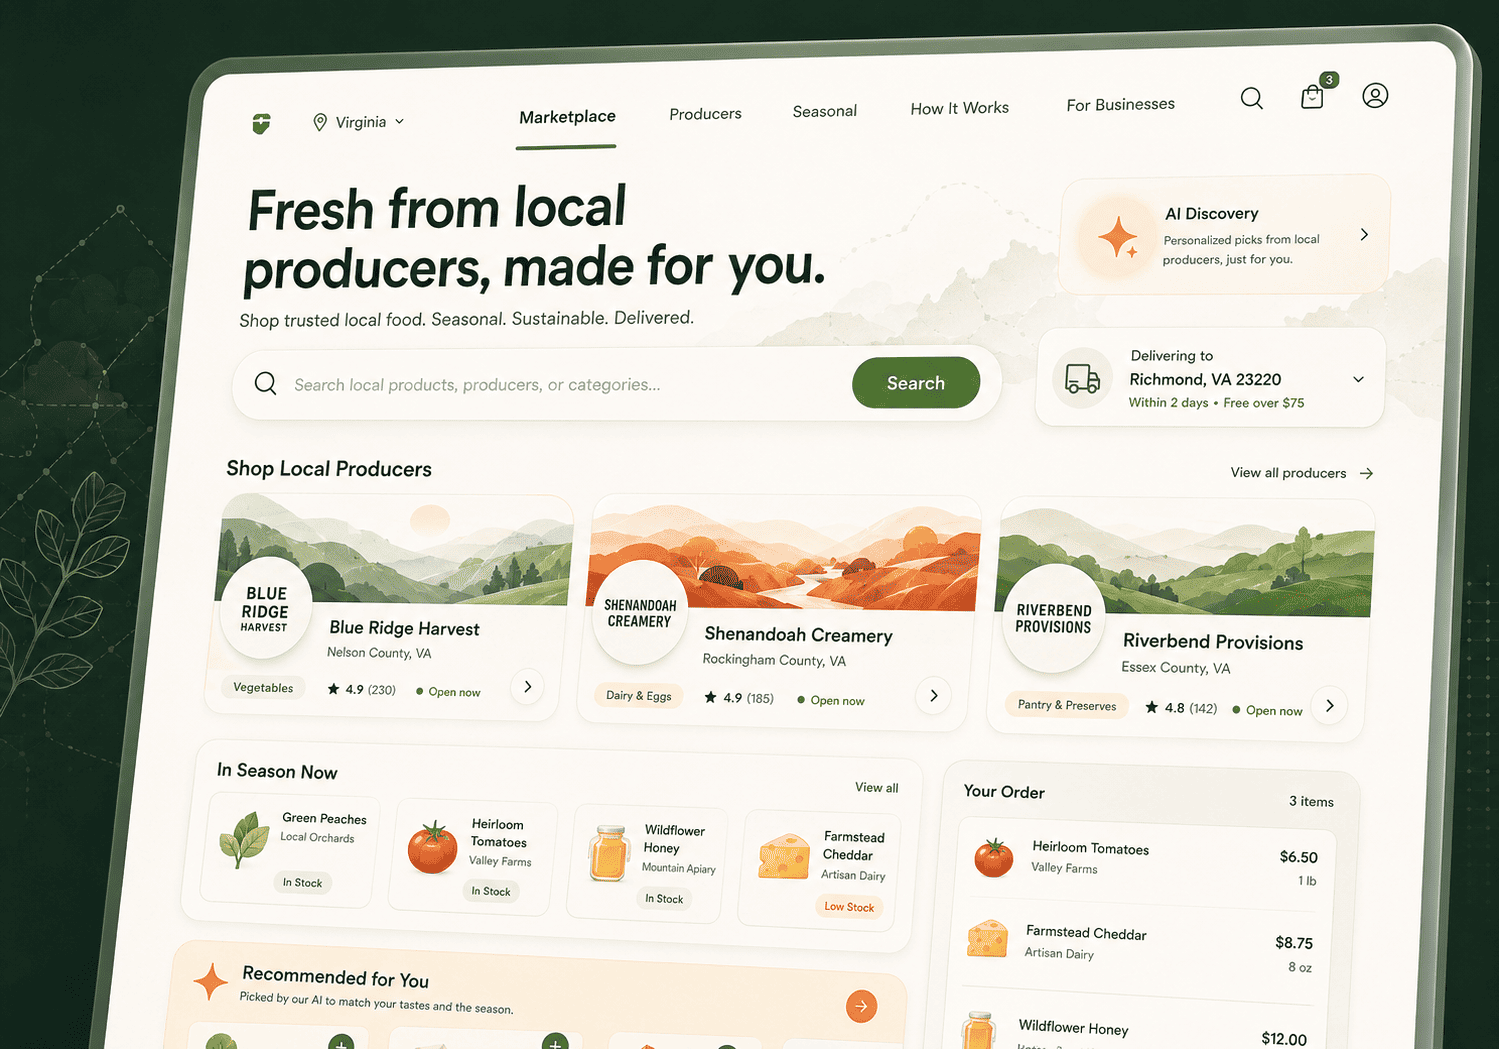
Digital Marketplace for Virginia Farmers, Local Producers & Direct-to-Consumer Food Sales

Plavno developed a custom multi-vendor marketplace for Virginia-based farmers, food producers, and regional sellers to unify product listings, vendor operations, customer ordering, and local fulfillment workflows.

Read More
3x

increase in product discovery relevance

Digital Marketplace for Virginia Farmers, Local Producers & Direct-to-Consumer Food Sales

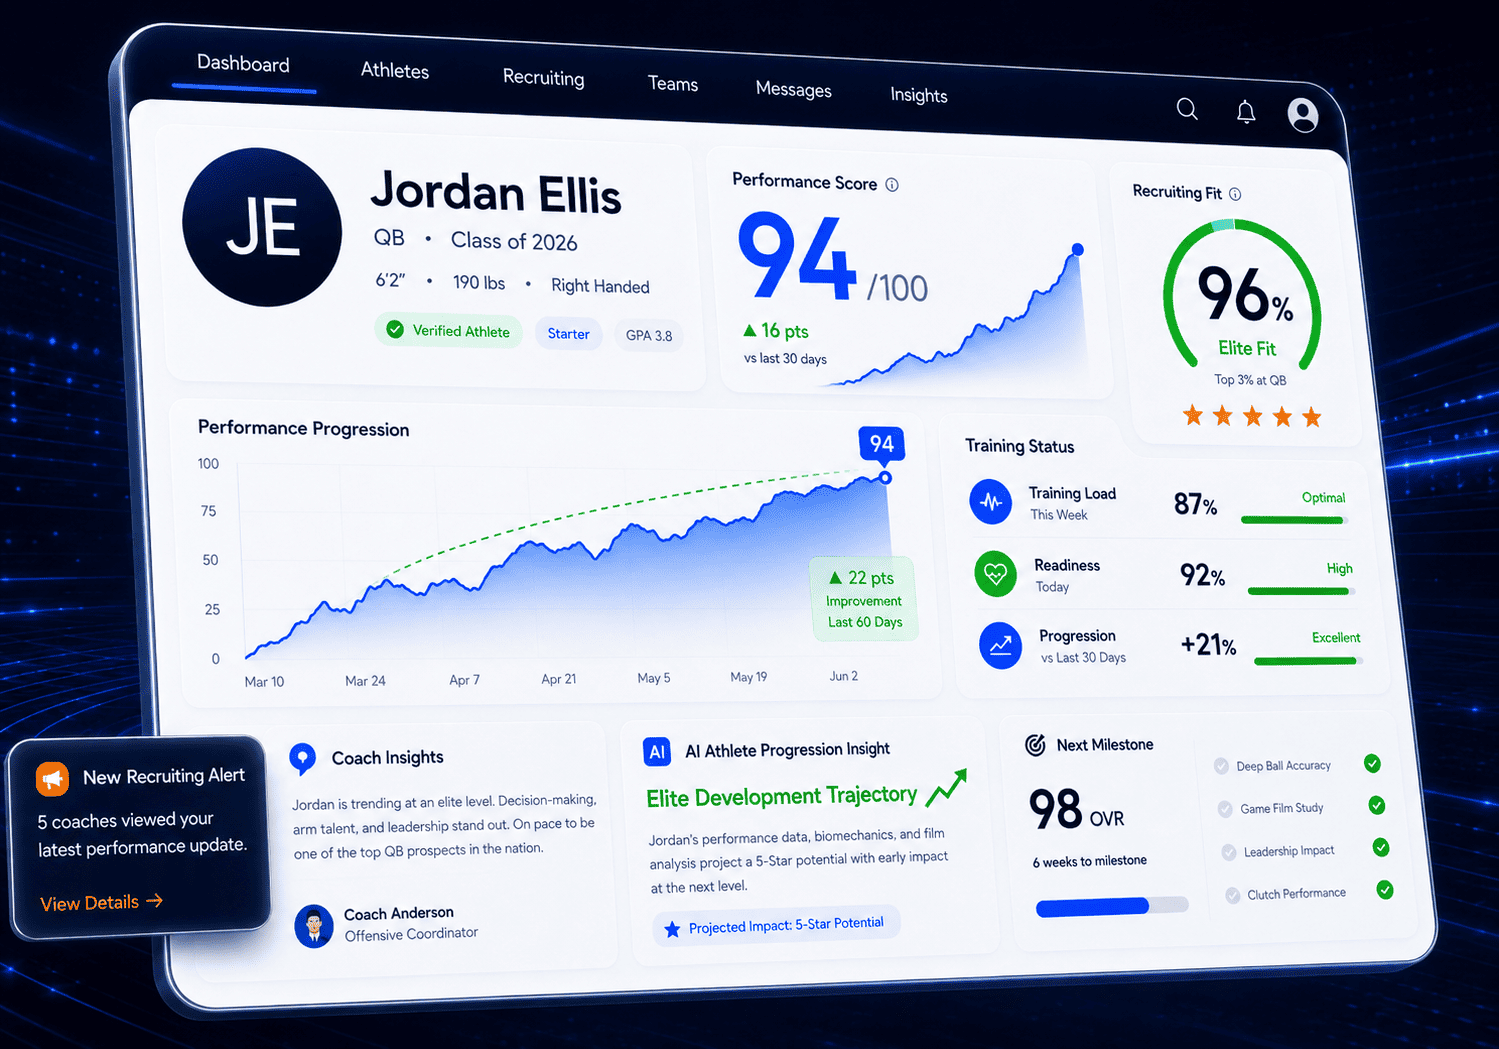
AI-Powered Sports Performance & Recruiting Platform for Virginia Clubs, Academies & Youth Programs

Plavno developed a custom sports technology platform for Virginia-based clubs and academies to combine athlete performance tracking, coach communication, recruiting workflows, and mobile engagement in one ecosystem.

Read More
3x

faster recruiting pipeline

AI-Powered Sports Performance & Recruiting Platform for Virginia Clubs, Academies & Youth Programs

Healthcare AI Solutions for Hampton Industries

Hampton Roads use cases that pay their keep

These patterns map to real employers and care networks from the shipyard to military-connected clinics across the region.

Hospital Handoffs

Hospital Handoffs

Transfer summaries

Hospital systems on the Peninsula

Triage and bed staffing fight noisy handoff notes every shift. AI drafts structured transfer summaries and flags incomplete med lists before the patient moves. Charge nurses review in one pane. Result is fewer bounce-backs between units and cleaner census data for commanders. Technically, retrieval over unit protocols plus template-constrained generation keeps language local. One network target is a third fewer after-hours catch-up notes within a quarter of go-live when baseline overtime is measured first.

Military Clinics

Military Clinics

Referral checks

Military-connected clinics

Families in Hampton hop between on-base and civilian care. Eligibility and referral rules confuse front desks. Agents pre-check coverage docs and draft referral packets against program criteria. Staff fix only exceptions. Patients wait less at check-in. The stack uses document extractors plus rule engines with full audit on every decision path. Sites often reclaim several minutes per visit once the first twenty high-volume visit types are covered.

Choose on engineering depth

Why Hampton buyers pick deep delivery

Generic shops demo models. We ship governed services with co-owned risk and proof from live operations.

Generic Agencies
Our Platform (Deep Engineering Expertise)
HIPAA-ready architecture from week one
checkmark
Gold-set evaluation before any pilot users
checkmark
EHR and claims system integration experience
checkmark
checkmark
Retrieval over approved clinical sources
checkmark
Token and infra cost budgets in production
checkmark
Slide-only strategy without build path
checkmark
Post-launch drift and override monitoring
checkmark

Testimonials

We are trusted by our customers

“They really understand what we need. They’re very professional.”

The 3D configurator has received positive feedback from customers. Moreover, it has generated 30% more business and increased leads significantly, giving the client confidence for the future. Overall, Plavno has led the project seamlessly. Customers can expect a responsible, well-organized partner.

Sergio Artimenia

Commercial Director, RNDpoint

Sergio Artimenia

“We appreciated the impactful contributions of Plavno.”

Plavno's efforts in addressing challenges and implementing effective solutions have played a crucial role in the success of T-Rize. The outcomes achieved have exceeded expectations, revolutionizing the investment sector and ensuring universal access to financial opportunities

Thien Duy Tran

Product Manager, T-Rize Group

Thien Duy Tran

“We are very satisfied with their excellent work”

Through the partnership with Plavno, we built a system used by more than 40 million connected channels. Throughout the engagement, the team was communicative and quick in responding to our concerns. Overall, we were highly satisfied with the results of collaboration.

Michael Bychenok

CEO, MediaCube

Michael Bychenok

“They have a clear understanding of what the end user needs.”

Plavno's codes and designs are user-friendly, and they complete all deliverables within the deadline. They are easy to work with and easily adapt to existing workflows, and the client values their professionalism and expertise. Overall, the team has delivered everything that was promised.

Helen Lonskaya

Head of Growth, Codabrasoft LLC

Helen Lonskaya

“The app was delivered on time without any serious issues.”

The MVP app developed by Plavno is excellent and has all the functionality required. Plavno has delivered on time and ensured a successful execution via regular updates and fast problem-solving. The client is so satisfied with Plavno's work that they'll work with them on developing the full app.

Mitya Smusin

Founder, 24hour.dev

Mitya Smusin

Maturity without theater

Raise autonomy only when metrics earn it

A four-level maturity climb keeps risk matched to control. Each level unlocks only after measured gains on the last.

Clipboard
Team
01

Level 1: Assisted drafts (ongoing)

Humans trigger every run. Models produce drafts only. Override reason codes feed weekly reviews. Success is time saved per artifact with quality stable. No auto-submit paths exist yet. Teams in Hampton often stay here for high-risk clinical prose for months.

02

Level 2: Queued suggestions (after gate)

The system precomputes work for morning queues. Staff still approve each action. Latency budgets and quiet hours protect night staff. You measure queue salvage rate and morning start backlog depth. Promotion needs two stable scorecard cycles.

Search in doc
Rocket
03

Level 3: Bounded auto-actions (selective)

Only low-risk steps run without a click. Examples include filing coded drafts or routing complete packets. Hard stops sit on safety and finance paths. Rollback is one flag. Audit samples expand for auto-actions by design.

04

Level 4: Cross-site playbooks (scale)

Winning workflows package as playbooks for sister clinics in Norfolk or Chesapeake. Config differs; core services stay shared. Governance boards review metric packs quarterly. Only then does multi-site live traffic expand under one change program.

Before you sign a vendor

Readiness checks for Virginia AI buyers in 2026

  • Name the owner and veto rights — A clinical owner and a compliance owner both need hard stop power. Projects without dual veto stall after the first PHI debate. Write their names into the charter before kickoff. Budget time for weekly decision slots. Missing owners are the top delay we see with Hampton groups. Fix that before any SOW lands.

  • Inventory systems and data classes — List EHR modules, imaging, RCM, HR, and file shares that the workflow will touch. Mark PHI and who presently consents to access. Gaps here kill timelines more than model choice. Export samples under approved protocols only. Keep a single data dictionary so vendors cannot invent fields midstream. Update the list when shadow visits reveal shadow IT.

  • Define success as a measured delta — Pick time saved, denial rate, or first-pass yield with a current baseline. Agree on sample size and review cadence. Vanity accuracy with no baseline wastes the pilot. Publish the formula so finance and nursing share one story. Freeze the metric set for the pilot window. Change only through a signed change log.

  • Demand evaluation and residual risk writeups — Vendors must show gold-set scores, failure classes, and human override design. Reject pure demo videos. Ask how drift detection will work after month three. Force a table of known limits. Tie payment milestones to those artifacts. Store them with your compliance packet for external review.

  • Plan ops cash and staff load — Token spend, monitoring seats, and on-call coverage need line items. Automation rarely ends staffing overnight. Plan for trainers and super-users at each site. Capture residual manual steps so nobody claims magicsaved hours. Schedule a 45-day ops review before expanding volume. Put that clause in the SOW.

Vitaly Kovalev

Vitaly Kovalev

Sales Manager

Get a Hampton Healthcare AI readiness audit

Share budget range, timeline, stack, and dataset scope. Receive a scored readiness audit and ballpark estimator built for Hampton and Hampton Roads providers.

Talk to Experts
Eugene Katovich

Eugene Katovich

Sales Manager

Need a custom software solution? We’re ready to help!

Plavno has a team of skilled developers ready to tackle the project. Ask me!

Get a Free Quote

Straight answers

Healthcare AI questions from Hampton buyers

Practical detail on cost, time, data, quality, compliance, and what happens after launch in Virginia care settings.

What drives the cost of Healthcare AI for Hampton providers?

Cost tracks workflow risk, data access friction, and integration depth more than brand of model. Simple staff knowledge agents with approved PDFs cost less than closed-loop clinical drafting inside a multi-site EHR. Hampton Roads groups often pay more when labs, imaging, and RCM each own separate identity systems. Budget for discovery, gold-set labeling, private networking, and a 90-day ops window, not only build sprints. Local rate cards reflect US engineering talent and compliance overhead. Expect discovery and PHI mapping as a fixed first package. Pilot build ranges with the number of systems touched and the severity of failure modes. Production hardening adds SSO, audit export, monitoring, and runbooks. Change boards and BAAs inject calendar time that pure software shops underquote. Ongoing cost is tokens, hosting, and human review on exceptions. Full auto paths raise audit sample rates. Partial assist paths keep humans in the loop and often net better risk balance. We price retainers against measured traffic, not vague seat counts. That keeps spend honest after month two when usage climbs. You can cut cost by starting with one high-volume workflow and one site. Expand only after baseline deltas prove out. Share budget, timeline, stack, and dataset scope early. We return a written estimate with assumptions you can challenge. Get Healthcare AI cost estimate in 24 hours when those four inputs arrive complete.

How long does it take to build Healthcare AI software?

A contained MVP for a single workflow often lands in eight to twelve weeks after data access is granted. That span covers discovery, gold sets, pilot, and hardening for a limited user group. Full multi-site deployment with mature maturity levels stretches across two or more quarters. Calendar time expands when EHR vendors throttle API access or when medical staff score samples slowly. Timeline risk concentrates in weeks one through four. If labels lag or systems lack sandboxes, models wait idle. We sequence demo-safe synthetic work so engineers stay busy while agreements clear. Parallel tracks for security review and UX training keep the critical path short. Fixed gates stop scope creep from eating the date. MVP means assisted drafts with human approval, logging, and basic scorecards. Full deployment means SSO mastery, cost budgets, drift monitors, and playbooks other clinics can adopt. Hampton groups that start small and publish weekly metrics tend to hit the shorter band. Groups that demand multi-facility launch day one rarely do. Plan buffer around holidays and survey seasons when clinical reviewers vanish. Publish the number of reviewer hours needed up front. Build contingency only after true blockers appear. We will not promise a date that depends on a third party logging us in. Written dependencies keep every party honest about slip risk.

What data do you need before a Healthcare AI project starts?

We need a workflow map, sample artifacts, role definitions, and consent paths for any PHI. Prefer redacted or synthetic sets first if BAA terms still sit in legal. For note assist, collect templates, sample notes with outcomes you accept, and prior errors you want fewer of. For RCM work, denials reason codes and clean claims samples matter more than raw claim dumps. Schema docs, retention rules, and identity sources come next. Who may see which field dictates retrieval and logging design. Missing retention policy freezes storage choices. Missing SSO details blocks any realistic pilot UI. Share vendor contact names for EHR interfaces so calendar invites do not stall. Quality labels beat volume. A few hundred carefully scored examples outrun ten thousand weak ones for early models. Rubric language must match how auditors will later grade the system. We help clinicians write that rubric so scoring stays fair. That method echoes how we ran rubric-based evaluation on the AI grader project for consistent feedback at scale. If data lives across Norfolk clinics and Peninsula hospitals under separate entities, name the legal route to combine samples. Multi-entity work needs early counsel. Do not scrape production stores without written clearance. We will help draft the minimum data package so collectors know exactly what to pull and what to leave sealed.

How do you evaluate quality for medical AI systems?

Quality is task success under operational constraints, not a single accuracy number. We define acceptance on a gold set with multi-rater review, then track live override rates, time saved, and safety incidents. For guided generation, faithfulness to retrieved sources scores separately from prose polish. For classification or coding, precision on high-cost error classes beats headline F1. Evaluation starts before models train. Clinicians agree on rubrics. Edge cases load intentionally. Each release reprints scorecards against that fixed set plus a fresh shadow sample. Drift shows when live distributions shift away from the gold set. We freeze release candidates that drop below agreed floors. Human factors sit inside quality. If nurses ignore the tool, the score is zero even if offline metrics shine. We instrument open rates, edit distance, and abandonment. UI friction is a defect. Training gaps are a defect. Tracking both keeps the program honest after the launch party ends. Virginia buyers often face external audits. We export evaluation packets with version pins, sample IDs, and residual risk notes. That package supports board questions and insurer reviews. Continuous sampling continues after launch so quality claims age with the system. Blind re-scores by new reviewers catch silent drift in labeling standards themselves.

How do you handle HIPAA and security for Healthcare AI in Virginia?

Security design begins with data classification and least-privilege paths. PHI never lands in unmanaged tools. Private networking, encryption, and vault-stored secrets are baseline. BAAs cover subprocessors before traffic flows. Access logs capture who prompted what and when. Retention and purge jobs match policy, not convenience. We separate training stores from inference logs. Removal requests and legal holds have runbooks. Role maps mirror your HRIS groups so joggers do not keep production access. Pen tests and tabletop incident drills support launch readiness. Findings close under tracked tickets with owners and dates. Model vendors and self-host choices both face review. Some groups prefer private endpoints; others accept contracted cloud under strict terms. We document the trade for latency, cost, and residual risk. No silent training on your prompts unless contracts say so and counsel agrees. Virginia providers also answer state privacy expectations and payer security questionnaires. We fill those packets with architecture diagrams that match deployed reality. Smoke tests after each change catch config drift that would fail a surprise audit. Continuous compliance is part of ops, not a once-a-year binder exercise hung on a shelf.

Contact Us

This is what will happen, after you submit form

Need a custom consultation? Ask me!

Plavno has a team of experts ready to start your project. Ask us!

Vitaly Kovalev

Vitaly Kovalev

Sales Manager

Schedule a call

Get in touch

Fill in your details below or find us using these contacts. Let us know how we can help.

No more than 3 files may be attached up to 3MB each.
Formats: doc, docx, pdf, ppt, pptx, xls, xlsx, txt.
Send request