bg image
bg image

Serving fredericksburg & virginia

Cut clinical admin load across fredericksburg care teams in 2026

Fredericksburg health systems still lose hours each day to chart chasing and intake rework. That delay hits revenue, staff retention, and patient wait times. We build Healthcare AI that removes repeat tasks from your front desk, nursing stations, and back office. It is for multi-site clinics, specialty groups, and operators growing past their first EHR year. You keep control of budget, timeline, and data scope from day one. Get Healthcare AI cost estimate in 24 hours. We map outcomes to your real workflows, not a slide deck. Clear milestones. Measurable relief on the floor.

Discuss Project

Overview

Why fredericksburg clinics still drown in chart work

Fredericksburg sits between regional hospitals, specialty practices, and military-adjacent care along I-95. Staff spend mornings reconciling referrals, scanning results, and answering the same benefit questions. Those tasks do not need another full-time hire. They need focused Healthcare AI services that read documents, route requests, and surface answers inside tools people already use. Trusted Healthcare AI Partner for Fredericksburg Businesses means we start from your pain points, not a product catalog.

Providers in Spotsylvania, Stafford, and King George face the same squeeze. Prior auth volume rises. Nurses document after hours. Call centers bounce callers between queues. We work with US-based clients, including companies operating in Virginia. Our goal is fewer handoffs and cleaner data before a claim leaves the building. That is the operational win leaders can measure without waiting on a multi-year program.

Technical approach stays practical. We combine retrieval-backed answers, structured extraction from clinical packets, and workflow hooks into your scheduling and support systems. For vision-heavy intake and imaging triage paths, our computer vision work pairs with language models so paper and phones stop blocking care teams. Security reviews and access controls stay in the critical path, not a late checklist.

We ground design choices in shipped work, not theory. An internal support agent project used LLM routing, enterprise search, and retrieval-augmented answers to cut knowledge lookup time for staff. An education grader project showed how rubric-based scoring and feedback generation hold consistency at volume. Those same patterns apply when Fredericksburg operators need consistent intake scoring or policy Q&A at scale. 10+ Healthcare AI projects delivered in US market guide how we sequence risk, data prep, and pilot scope for Virginia sites.

Talk to an Expert
Document extraction

Read clinical packets

OCR + structured extraction from referrals, results, and intake forms

Route requests

Route & prioritize

Workflow hooks into scheduling, support queues, and auth paths

Retrieval answers

Answers in your tools

Retrieval-backed policy Q&A inside EHR and staff systems

Security controls

Security on the path

Access controls, PHI redaction, and audit logs from day one

Core clinical stack

Architecture fredericksburg teams can run day one

Clients in Fredericksburg receive a production path, not a demo notebook. We design agents and pipelines that sit beside the EHR, PACS, and ticketing tools you already pay for. Core pieces include a retrieval layer over approved knowledge, structured extraction for packets and forms, and guarded action steps that only fire with clear human ownership. Every claim below ties to patterns we already shipped in enterprise support agents and high-volume scoring systems.

Language models handle free-text routing and draft responses. We pick model tiers by task risk. High-stakes clinical language stays on stronger models with logging. Low-risk administrative chat can use lighter models to control spend. Retrieval-augmented generation keeps answers tied to your policies, order sets, and SOPs. That choice came directly from building an internal knowledge assistant where staff needed enterprise search plus workflow automation, not fuzzy chat alone.

Document and image paths matter for voter-registrystyle intake piles you see in multi-clinic groups across Caroline and Culpeper corridors. OCR plus classification sends packets into the right queue. Extraction maps fields into appointment, billing, or case objects. We expose those steps as services so engineering can version and monitor them. Rubric-style evaluators, proven in our AI grader work for consistent scoring and richer feedback, help QA thrift of draft summaries before staff publish them.

Security/compliance is part of the build, not a sticker. Role-based access, audit logs, PHI redaction before external calls, and environment separation land in the first sprint plan. We map controls to HIPAA expectations and your own risk register. Secrets stay in managed stores. Training data never silent-mailed to personal accounts. Vendors get least privilege only.

DevOps keeps pilots from rotting. Infrastructure as code, staged promote paths, feature flags, and health checks travel with the first feature. We instrument latency, token cost, retrieval hit rate, and human override rate. On-call runbooks name who owns a drift alert. That operational spine is why enterprise Healthcare AI implementation survives the second clinic rollout instead of dying after a pilot party.

plavno logo

Build your first
Smart AI project today!

Just tell the Plavno AI Agent about your project - it will ask questions, gather requirements, and propose a tailored solution

Healthcare AI Solutions for Fredericksburg Industries

Local care ops that repay within one budget cycle

Use cases map to Fredericksburg hospitals, specialty groups, and regional operators along the Rappahannock corridor. Each item ties to a concrete workflow and payback path.

Chart Backlog

Chart Backlog

Hospital notes

Hospital systems reducing chart backlog

Mary Washington-area inpatient and ambulatory teams still battle after-visit documentation debt. Night staff copy notes from paper packets into the EHR under time pressure. We deploy extraction plus draft-summary agents that prepare structured notes for clinician edit. Staff close charts faster and cut overtime spikes. One patterned ROI target is 25% fewer after-hours charting hours in the first quarter after pilot expand. Technically, packet OCR feeds a retrieval layer. A guarded LLM drafts under section templates with full audit trails.

Prior Auth

Prior Auth

Specialty clinics

Specialty clinics clearing prior auth queues

Ortho, cardio, and imaging practices near Central Park lose days waiting on incomplete packets. Schedulers chase faxed criteria lists by phone. Our queues classify auth packets, flag missing fields, and draft payer narratives from your templates. Turnaround on first-pass submissions improves and denials for incomplete data drop. Plan for roughly 30% fewer status-chase calls within 90 days of go-live when data quality is stable. The pipeline joins classification models with rules engines and staff override workflows.

Military Practices

Military Practices

Benefit answers

Military family practices near Quantico lanes

Practices serving transfer families deal with fragmented records and benefit questions. Front desks repeat TRICARE guidance all day. We build retrieval agents over your approved benefit scripts and location policies. Answers stay consistent and cite sources staff can verify. Expected gain is shorter average handle time on intake calls without adding headcount. Architecture mirrors our enterprise employee support agent with LLM routing, enterprise search, and retrieval-augmented answers behind your existing phone tree.

Long-term Care

Long-term Care

Daily briefs

Long-term care operators across Stafford

Facilities track med changes, family updates, and state reporting with sparse IT bench strength. Missed notes create survey risk. We implement structured event capture and daily brief generators for charge nurses. Leadership sees exceptions earlier and reduces surprise survey findings. A practical ROI is fewer late filings and less weekend scramble for documentation. Event logs feed rubric-style checks inspired by our AI grader design so consistency holds across shifts.

Home Health

Home Health

Visit capture

Home health coordinators in Spotsylvania

Coordinators juggle visit notes, supply orders, and payer rules while driving between homes. Mobile data entry errors pile up. We ship mobile-friendly capture with offline draft and delayed sync. Agencies improve visit close rates and reduce claim rework. Target outcome is a measurable drop in incomplete visit packets week over week after training. Stack uses lightweight clients, queue workers, and validation services that respect rural connectivity.

Billing Groups

Billing Groups

Denial appeals

Regional billing groups near Fredericksburg

Independent billing shops process claims for multiple Virginia practices with thin margins. Denial letter variance sinks cash flow. We add denial classification, root-cause tags, and suggested appeal drafts grounded in your playbooks. Collectors spend time on dollars that move, not sorting mail. Aim for faster first-pass appeals and cleaner aging buckets inside two billing cycles. Models classify free text, village score confidence, and route low-confidence items to seniors only.

Case Study

We help customers cut
down on development

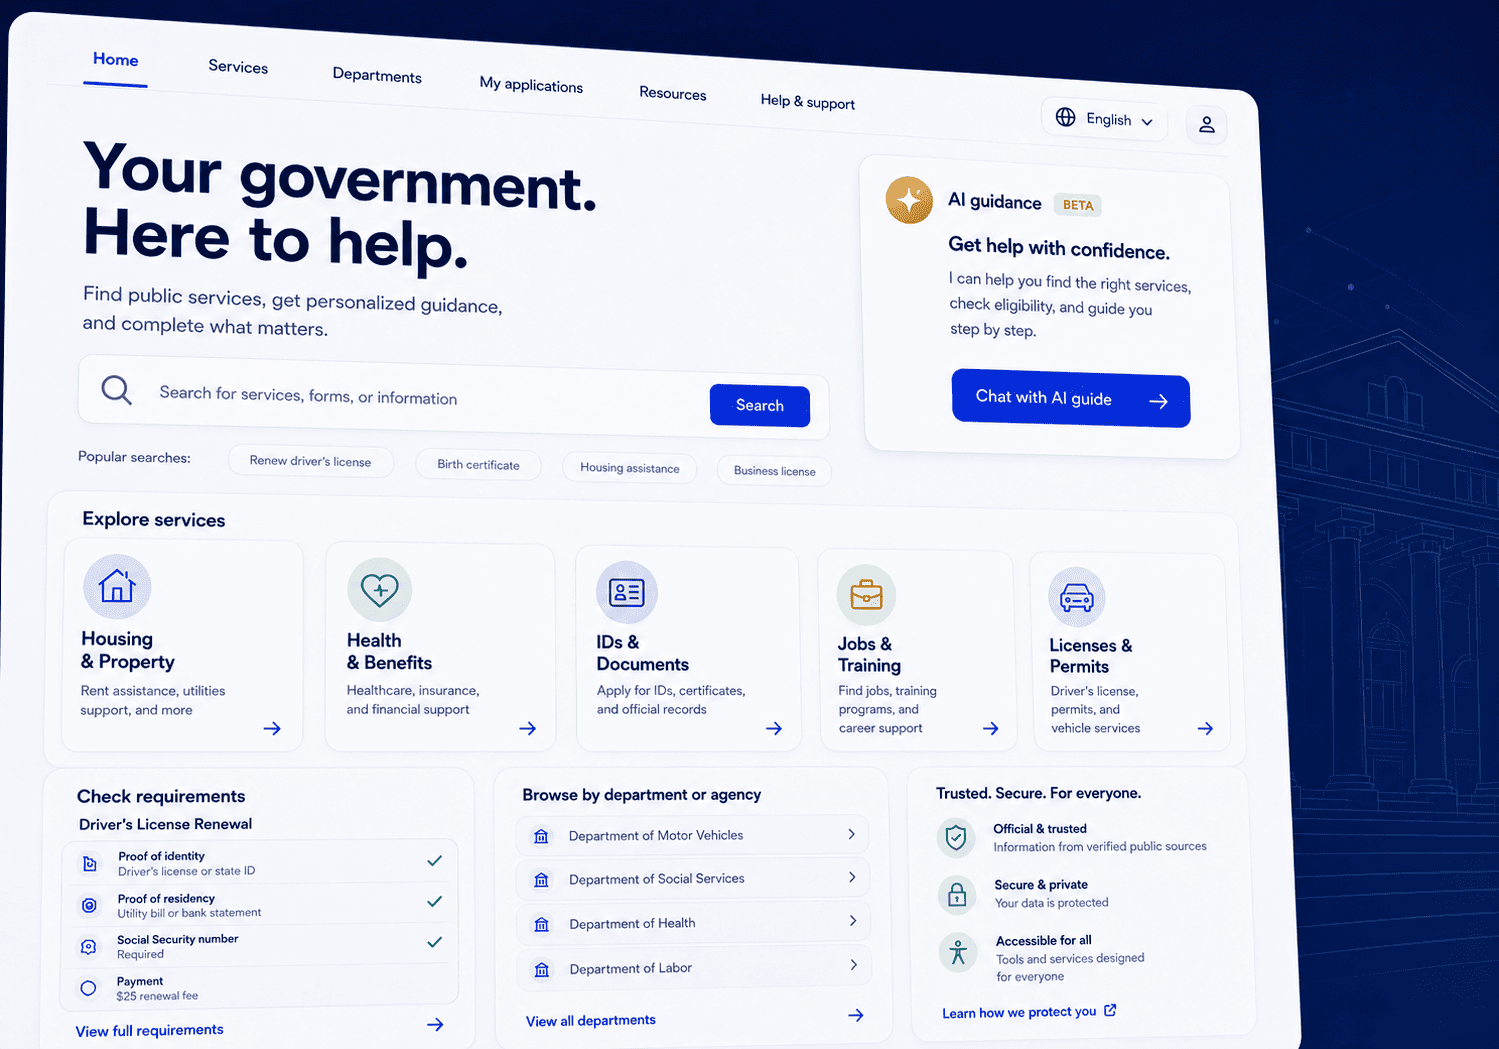
AI-Powered Citizen Services Website Platform for Virginia State Agencies

Plavno developed a modern eGovernment website platform for Virginia state agencies that centralizes citizen services, public information, department content, and an AI-powered guidance agent in one scalable system.

Read More
70%

reduction in routine citizen inquiries to agency staff

AI-Powered Citizen Services Website Platform for Virginia State Agencies

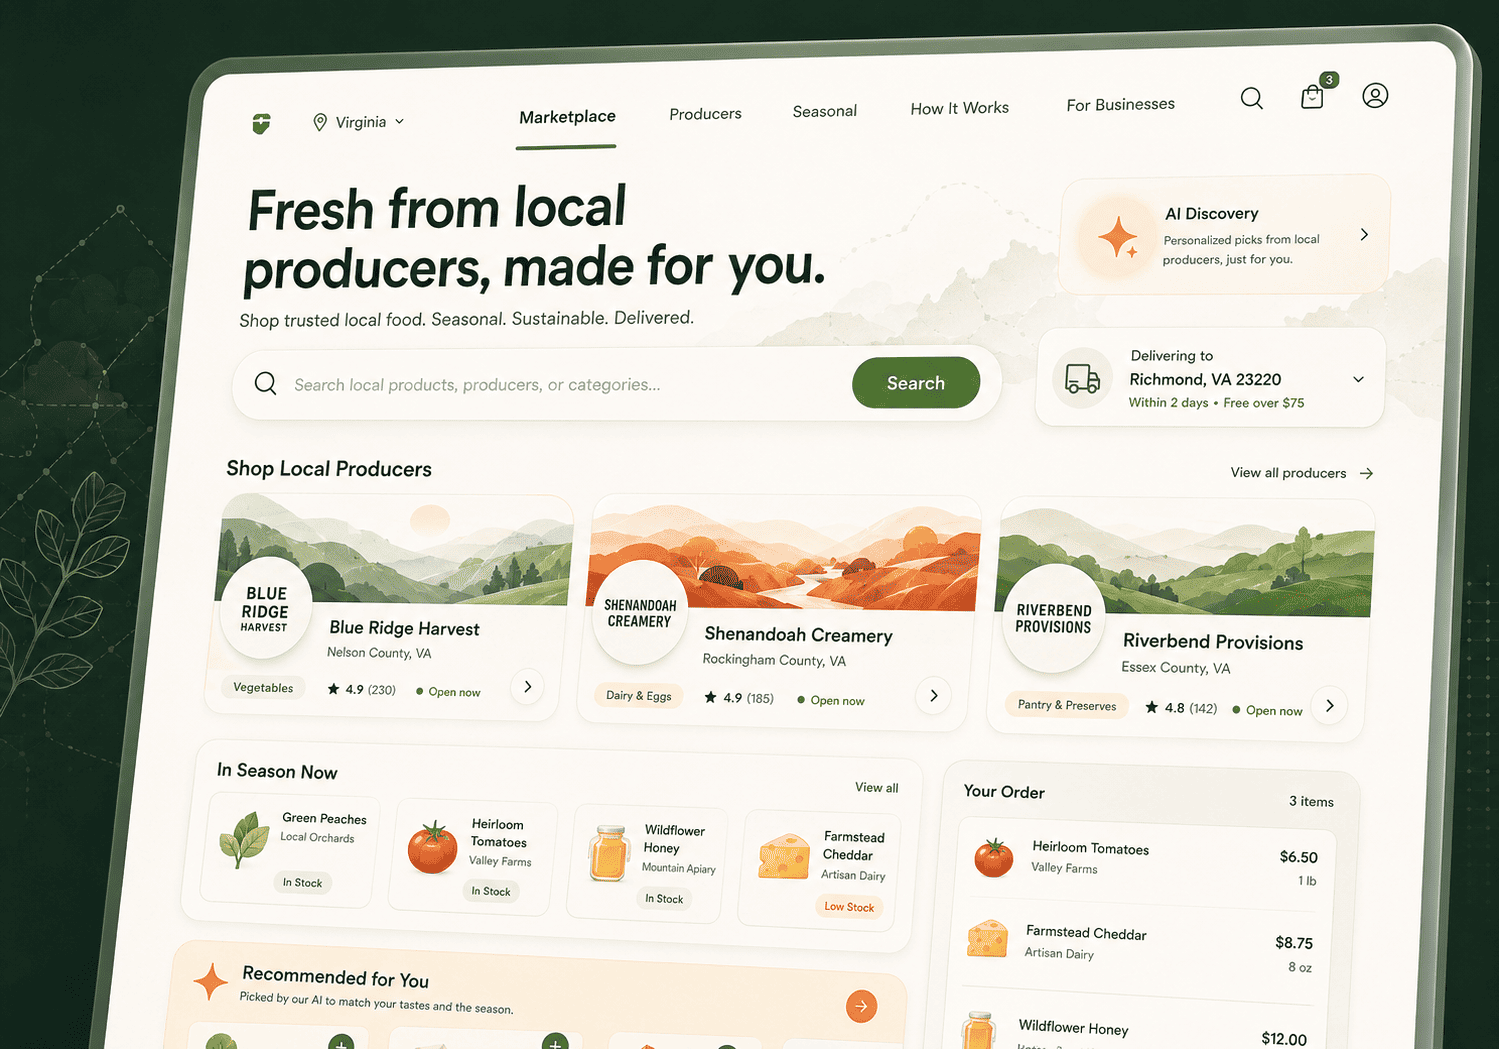
Digital Marketplace for Virginia Farmers, Local Producers & Direct-to-Consumer Food Sales

Plavno developed a custom multi-vendor marketplace for Virginia-based farmers, food producers, and regional sellers to unify product listings, vendor operations, customer ordering, and local fulfillment workflows.

Read More
3x

increase in product discovery relevance

Digital Marketplace for Virginia Farmers, Local Producers & Direct-to-Consumer Food Sales

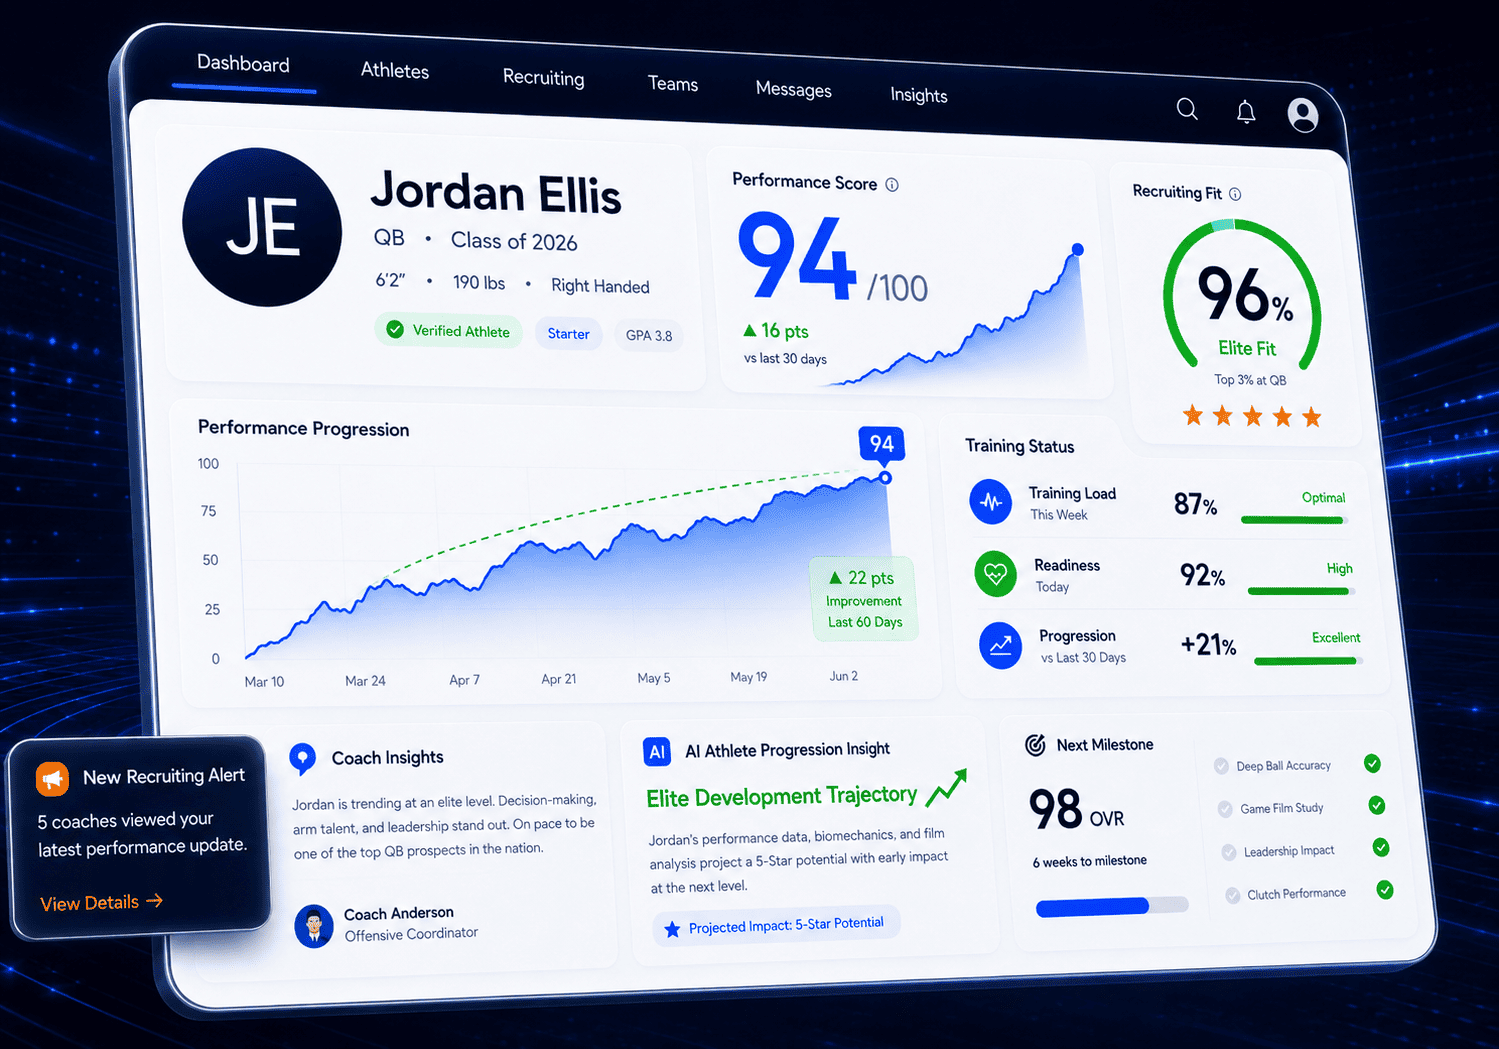
AI-Powered Sports Performance & Recruiting Platform for Virginia Clubs, Academies & Youth Programs

Plavno developed a custom sports technology platform for Virginia-based clubs and academies to combine athlete performance tracking, coach communication, recruiting workflows, and mobile engagement in one ecosystem.

Read More
3x

faster recruiting pipeline

AI-Powered Sports Performance & Recruiting Platform for Virginia Clubs, Academies & Youth Programs

Architecture & Engineering Overview

What fredericksburg leaders should demand before signing

Hours returned

Hours & cash recovered

Price AI against overtime, temp staffing, and delayed cash — chart close and first-pass auths

Narrow pilots

Narrow start points

One workflow, baseline sample, expand only after staff accept drafts — grader-style acceptance

Cost control

Predictable unit cost

Token budgets, retrieval caching, overnight batching with weekly spend-to-outcome reviews

Vendor exit

Your repos, clean exit

Prompts, code, and eval sets live with you; exit clauses and data return in the SOW

For Business: Technical ROI & Risk Mitigation

ROI comes from hours returned and denials avoided, not model novelty. Fredericksburg operators should price Healthcare AI against overtime, temp staffing, and delayed cash. When chart close time drops, you free clinicians without cutting headcount skill. When auth packets complete on first pass, cash lands earlier. Those are ledger lines finance trusts.

Risk mitigation starts with narrow start points. We isolate one workflow, define a baseline sample, and only expand after staff accept the drafts. That volume-tested discipline showed in our AI grader project where consistent scoring and richer feedback had to hold at scale. The same acceptance bar applies when nurses review AI-prepared summaries.

Cost control is explicit. Token budgets, caching of retrieval chunks, and batching for overnight jobs keep unit cost predictable. Leaders see spend next to outcome metrics each week. If a queue burns budget without quality gains, we throttle or redesign the step before splashy expansion.

Vendor risk drops when code, prompts, and evaluation sets live in your repos. You are never locked to a slide brand. Exit clauses and data return plans sit in the statement of work up front. That matters for multi-site groups that may change policy after a clinical system swap.

Local context matters for staffing. Rural and suburban clinics around Fredericksburg cannot absorb long training classes. Interfaces must feel like the tools people already open. Adoption risk falls when we embed drafts inside existing EHR tabs or simple side panels rather than forcing another login.

1

Data contracts & failure budget

Identity mapping, read-only vs dual-control writes, and human-approve gates defined before prompts

2

Shadow → assisted → automated

Risk register, integration map, and client governance boards at each promotion gate

3

Flags, canaries, observability

Single-clinic rollouts, accuracy samples, latency and override-reason drift reviews on calendar

4

Transfer with runbooks

Prompt change process, escalation paths, and ownership handoff after stabilization window

For CTOs: Architecture & Technical Lifecycle

Lifecycle control beats one-off pilots that never reach production ownership. Kickoff starts with data contracts, identity mapping, and a failure budget. We define what wrong looks like before writing prompts. Decision points include which systems are read-only, which write under dual control, and when humans must approve actions.

Discovery produces a risk register, integration map, and pilot success metrics. Build stages move from shadow mode to assisted mode to limited automated actions. Governance boards on the client side review promotion gates. That staged growth mirrors how we rolled enterprise search agents into daily support work without shocking staff.

Trade-offs stay visible. Stronger models mean higher cost on clinical language. Lighter models need tighter retrieval and more rules on admin tasks. Batch jobs reduce peak latency stress on daytime clinics. CTOs choose the mix with full cost models, not surprise invoices.

Release discipline uses feature flags, canaries on single clinics, and rollback plans that staff understand. Observability covers accuracy sample sets, latency, and override reasons. Drift reviews run on a calendar, not only after complaints.

Post-launch ownership is documented. Your team receives runbooks, prompt change process, and escalation paths. We stay for stabilization then transfer day-to-day monitoring signals into your tools. Technical debt stays listed with owners, not buried in chat threads.

Retrieval layer

Dense + keyword retrieval

Structure-aware chunking over policies and order sets so rare local protocol wording still surfaces

Orchestration

Schema-strict orchestration

Agents draft, classify, fetch only — no invented write paths; human gates live in code

Rubric eval

Rubric scoring harness

Gold-set eval for extraction and faithfulness; grader-style bounds on tone, length, completeness

Integrations

FHIR, queues, defensive OCR

Stable APIs, message queues for fax spikes, PHI redaction before external calls, confidence stored

For Engineers: Implementation Details & Stack

Stack choices favor inspectable pipelines over black-box platforms. Retrieval layers use dense plus keyword search so rare local protocol wording still surfaces. Chunking follows document structure from policies and order sets instead of naive token splits. That design came from enterprise knowledge assistant work needing precise source answers rather than generic chat tone.

Orchestration services manage tool calls with strict schemas. Agents may draft, classify, or fetch. They do not invent write paths. Human approval gates sit in the code, not only documentation. Evaluation harnesses score gold sets for extraction fields and answer faithfulness before each release.

For graded or scored outputs, we reuse rubric patterns proven in the AI grader for EdTech. Rubrics keep nurse forwarded summaries within length, tone, and completeness bounds. Feedback generation attaches short rationales staff can scan quickly. Edge cases like conflicting labs get forced to human review with reasons attached.

Integration code prefers stable APIs, FHIR where available, and message queues for bursty fax or scanner inflows. We keep secrets out of containers. PHI redaction steps run before any external model call when policy requires. Async workers keep interactive apps snappy during batch packet nights.

Local lag and scanner quality around multi-site groups force defensive OCR. We store confidences and allow staff corrections that retrain nothing by accident without an explicit data loop. Logging levels stay high enough for audits yet filtered enough to protect privacy.

Controlled cloud

Customer-controlled deploy

Approved regions, env separation, KMS keys, time-bound access, egress-limited networks

HIPAA controls

HIPAA & BAA path

Least privilege, synthetic lower envs, break-glass session recording, approved subprocessors

Monitoring

Live quality signals

Latency, empty retrievals, token spend, override spikes — weekly clinician sample reviews

Incident response

Patient-safety playbooks

Severity classes, provider-outage fallbacks, version-tagged prompt and rule fixes after incidents

Cost budgets

Per-clinic cost dials

Budgets by workflow, idle scale-down, separate night-batch limits so multi-site spend stays calm

Environments

Boring PHI fabric

Encryption, tokenization where allowed, freshness monitors, and clear connector ownership

Infrastructure, Observability & Security

Production Healthcare AI lives or dies on monitored controls, not launch demos. We deploy into customer-controlled clouds or approved regions with separation of environments. Network policies limit egress. KMS-managed keys protect stores holding PHI. Access is time-bound and reviewed.

Compliance coverage includes HIPAA-aligned safeguards, BAAs with subprocessors you approve, and SOC2-minded process evidence when required. Training environments use synthetic or properly de-identified sets first. Production access is least privilege with session recording for break-glass cases.

Monitoring tracks report latency, error rates, retrieval empty hits, token spend, and human override ratios. Alerts page owners when override spikes or cost drifts. Weekly quality samples pull random outputs for clinician review on a fixed cadence.

Incident response names severity levels, patient-safety vs ops-only classes, and who speaks to clinical leadership. Playbooks cover model provider outages with cached fallbacks or graceful degradation to manual queues. Post-incident notes feed prompt and rule changes with version tags.

Cost control remains operational. Budgets per clinic and per workflow sit next to dashboards. Idle endpoints scale down. Night batch jobs carry different limits than daytime assistants. That keeps Fredericksburg multi-site rollouts from surprising finance after a quiet August.

Testimonials

We are trusted by our customers

“They really understand what we need. They’re very professional.”

The 3D configurator has received positive feedback from customers. Moreover, it has generated 30% more business and increased leads significantly, giving the client confidence for the future. Overall, Plavno has led the project seamlessly. Customers can expect a responsible, well-organized partner.

Sergio Artimenia

Commercial Director, RNDpoint

Sergio Artimenia

“We appreciated the impactful contributions of Plavno.”

Plavno's efforts in addressing challenges and implementing effective solutions have played a crucial role in the success of T-Rize. The outcomes achieved have exceeded expectations, revolutionizing the investment sector and ensuring universal access to financial opportunities

Thien Duy Tran

Product Manager, T-Rize Group

Thien Duy Tran

“We are very satisfied with their excellent work”

Through the partnership with Plavno, we built a system used by more than 40 million connected channels. Throughout the engagement, the team was communicative and quick in responding to our concerns. Overall, we were highly satisfied with the results of collaboration.

Michael Bychenok

CEO, MediaCube

Michael Bychenok

“They have a clear understanding of what the end user needs.”

Plavno's codes and designs are user-friendly, and they complete all deliverables within the deadline. They are easy to work with and easily adapt to existing workflows, and the client values their professionalism and expertise. Overall, the team has delivered everything that was promised.

Helen Lonskaya

Head of Growth, Codabrasoft LLC

Helen Lonskaya

“The app was delivered on time without any serious issues.”

The MVP app developed by Plavno is excellent and has all the functionality required. Plavno has delivered on time and ensured a successful execution via regular updates and fast problem-solving. The client is so satisfied with Plavno's work that they'll work with them on developing the full app.

Mitya Smusin

Founder, 24hour.dev

Mitya Smusin

Delivery capabilities

What fredericksburg operators actually receive in 2026

Workflow discovery that respects clinic time

Workflow discovery that respects clinic time

Leaders rarely know every exception that kills a queue. We shadow real shifts in Fredericksburg sites for short windows and map blockers with floor staff. The output is a ranked list of automatable steps with data readiness scores. It stops vanity pilots on rare edge cases. We use simple process tables first, tools second. Clinics keep ownership of priorities and freeze scope early.

Knowledge agents for staff questions

Knowledge agents for staff questions

Employees lose minutes hunting policy PDFs and outdated share drives. We build retrieval agents that answer from approved sources and cite them. This is the same pattern used in our enterprise employee support agent with LLM routing and enterprise search. Staff get faster first answers during busy peaks. Overrides become training signals. Content owners stay in charge of what is publishable.

Consistent scoring for multi-site reviews

Consistent scoring for multi-site reviews

When sites score charts or training cases differently, quality programs stall. We implement rubric-based evaluation and feedback generation patterns proven in our AI grader for EdTech. Leadership compares sites fairly without endless calibration meetings. Scores stay explainable. Human reviewers focus on edge cases. Virginia multi-site groups finally share one grader language across campuses.

Integration-first delivery with your EHR spine

Integration-first delivery with your EHR spine

AI that lives outside clinical systems gets ignored. We wire drafts and flags into the systems staff already open, using APIs and queue adapters. Failures fall back to safe quorumsstreams. Engineers leave you maintainable adapters, not hard-coded screen scrapers. Change control fits your existing release windows. Downtime plans stay written and tested.

Post-launch cost and quality controls

Post-launch cost and quality controls

Without budgets and sample reviews, model spend and quality drift quietly. We install dashboards for token cost, latency, and override reasons. Weekly sample audits catch quiet failures before patient impact. Flags throttle expensive paths during demand spikes. Your ops lead owns the dial. That discipline keeps Healthcare AI affordable after the press release fades.

Data & compliance fabric

How we harden PHI paths for virginia clinics

The second build concern after core agents is the data fabric under them. Fredericksburg groups often mix on-prem EHR modules, cloud imaging stores, and fax inflows no one owns. We start by inventorying sources, retention rules, and legal bases for each field. Without that map, models see junk and compliance voids appear later.

Integration plans favor stable interfaces. Where FHIR resources exist, we use them for allergies, medications, and encounters. Where they do not, we agree on batch extracts with freshness SLAs. Message queues absorb scanner spikes so daytime clinics stay responsive. Every connector logs lineage so a wrong address is traceable to a source system, not a vague AI blame.

Quality gates sit before training or retrieval indexing. De-duplication, field-level validation, and staff correction loops prevent silent garbage. We refuse to jackhammer dirty historical notes into production indexes. Shadow runs compare automatic extraction to clerk baselines until gap rates meet your bar.

Security work here is concrete. Encryption at rest and in transit, tokenization of identifiers where business allows, and environment isolation for lower environments. BAAs and processor lists are finalized before load tests with real samples. Access reviews run on a calendar suitable for multi-clinic Virginia operators who rotate contractors often.

Operational monitors watch data freshness, failed connectors, and redaction misses. Alerts hit the on-call channel with clear owners. Cost signals cover storage growth from scanned packets which can explode after a regional affiliation. Governance keeps the fabric boring and boring is how PHI work should feel after go-live.

Eugene Katovich

Eugene Katovich

Sales Manager

Need a custom software solution? We’re ready to help!

Plavno has a team of skilled developers ready to tackle the project. Ask me!

Get a Free Quote

Maturity path

From manual intake to assisted care ops in fredericksburg

A staged maturity model keeps risk low while value compounds. Each phase has exit criteria tied to staff acceptance, not vanity demos.

Clipboard
Team
01

Step 1: Baseline & data readiness (2 weeks)

We sample real queues from your Fredericksburg or Stafford sites. Volume, error types, and system ownership get written down. You receive a readiness score per workflow and a fixed pilot charter. No code ships until baselines and success metrics are signed. Timeline stays tight so leadership keeps focus. Deliverable is a go or no-go brief with cost bands.

02

Step 2: Shadow assistants only (3–4 weeks)

Models draft and classify while staff work as usual. Outputs never reach patients or payers yet. Reviewers score quality against rubrics each day. Metrics cover precision on fields and time saved estimate. You see truth without operational risk. Exit requires meeting the quality floor on the gold set for two stable weeks.

Search in doc
Rocket
03

Step 3: Assisted mode for live queues (3–5 weeks)

Drafts appear inside staff tools with one-click accept or edit. Override reasons are captured as structured tags. Training sessions run short and on-shift. Supervisors monitor dashboards daily. This phase proves adoption before any auto-send. Exit needs stable override rates under the agreed threshold and no safety incidents.

04

Step 4: Narrow automation with guards (2–4 weeks)

Only low-risk actions auto-complete under dual rules and logs. High-risk clinical language stays human approved. Cost caps and rate limits turn on. Runbooks for failures are drilled once. Expansion to a second site follows only after metrics hold. You leave with a production system, not a perpetual pilot tent.

Planning answers

Fredericksburg healthcare AI questions for 2026 buyers

Straight answers on cost, time, data, quality, security, and operations for Virginia care teams.

What drives the cost of Healthcare AI services for a Fredericksburg clinic?

Cost tracks scope, system complexity, and data readiness more than model brand names. A single-site specialty practice with clean intake PDFs spends far less than a multi-hospital group with fragmented EHR modules. Integration hours usually dominate vendor model fees after the first month. Local markets around Spotsylvania and Stafford often need scanner path cleanup before models see useful text, and that work must be budgeted honestly.

People costs include clinical reviewers during shadow mode and IT time for identity mapping. If you skip those, quality lags and overtime returns. Token and hosting fees stay controllable when you cache retrieval and limit high-power models to high-risk language. We publish weekly unit-cost reports so finance sees spend next to hours returned.

Compliance heavy paths cost more up front and less later: encryption layouts, audit logs, and BAAs. Cutting those corners creates larger legal and retrofit bills. Expansion discounts apply when the second clinic reuses the same connectors and rubrics without net-new custom code. Ask any vendor for line items that separate discovery, integration, model runtime, and support before you compare quotes.

How long does it take to build Healthcare AI software?

An MVP that shadows one workflow often lands in eight to twelve weeks when data is available and stakeholders meet weekly. Full assisted mode across a multi-site group can take four to six months depending on EHR access speed and change windows. Night claims batch work can ship earlier than interactive nurseside tools because release risk differs.

Discovery and baselines take the first two weeks. Shadow builds fill the next three to four. Assisted rollout needs staff training and at least two stable quality weeks before exit. Automation with guarded actions only starts after override rates look safe. Rushing those gates creates rework and distrust on the floor.

Delays most often come from unclear system ownership, missing BAA paperwork, or gold sets that no clinician has time to label. We protect the schedule by freezing pilot scope early and staffing short review slots. If you need a board demo earlier, we can show shadow quality dashboards without claiming production success. Timelines stay honest when success metrics are written before code starts.

What data do you need before starting Healthcare AI implementation?

We need realistic samples of the documents, tickets, or messages the system will see, not only clean templates. Include the messy scans and half-complete auth packets that clog meters in riverside clinics. Without those, models look fine in demos and fail on Mondays. Access maps for identifiers, roles, and systems of record come next so privacy reviews start early.

Labels or reviewers for a gold set are mandatory. Even fifty carefully scored samples beat thousands of unscored files. For retrieval agents, approve the policy corpus and mark which documents expire. Stale PDFs create confident wrong answers that staff learn to ignore. We also request volume stats by hour so infrastructure sizing matches real peaks around shift changes.

When data is sparse, we begin with synthetic nonsensitive patterns and escalate carefully. Clinics in King George or Culpeper sometimes start with de-identified extracts while legal finishes BAAs. Delaying forever is worse than a small, careful pilot on a low-risk queue. Data nominations list owners so updates continue after go-live instead of freezing knowledge at launch day.

How do you evaluate quality of Healthcare AI before wider rollout?

Quality is measured against gold sets and live override behavior, not demo applause. Extraction tasks track field-level precision and recall for the fields that actually move a claim or note. Answer tasks track faithfulness to sources, completeness against rubrics, and clinician edit distance. Latency and cost sit beside those scores because slow or expensive help gets unused.

Shadow mode produces side-by-side comparisons with staff work for fixed periods. We require stable pass rates for at least two consecutive review windows. Rubric-based scoring patterns, which we also used in education grading systems for consistent scoring and richer feedback, keep multi-reviewer judgment aligned. Disagreements get adjudicated and become new tests.

Live assisted mode watches override rates and codes why people change drafts. Rising overrides on one site signal a data or prompt drift issue. Random audits continue after launch on a calendar. We never treat launch as the finish line. Fredericksburg multi-site operators should demand the same scorecards across clinics so an expansion decision is numerical, not political.

How do you handle HIPAA, security, and compliance for medical AI?

Security design starts before models touch any PHI. We define environments, encryption standards, secret storage, and least-privilege roles in the plan of record. BAAs cover every subprocessor you approve. Logs hold who saw what and when. Redaction steps run before external calls when policy requires them. Training environments stay synthetic or properly de-identified first.

Operational controls include change management for prompts and rules, break-glass procedures, and session recording for elevated access. Hotels of tooling do not replace these basics. Incident severity models separate patient-safety events from ordinary outages so paging and communications match risk. Evidence packs support your compliance team during reviews instead of scrambling after a questionnaire lands.

Virginia providers serving military families or state programs may carry extra contractual constraints. We map those early and refuse shortcuts that block future contracts. Pen tests and access reviews run on cadence rather than once at launch. Security is part of healthcare AI consulting Fredericksburg VA buyers should treat as table stakes, not optional polish.

Contact Us

This is what will happen, after you submit form

Need a custom consultation? Ask me!

Plavno has a team of experts ready to start your project. Ask us!

Vitaly Kovalev

Vitaly Kovalev

Sales Manager

Schedule a call

Get in touch

Fill in your details below or find us using these contacts. Let us know how we can help.

No more than 3 files may be attached up to 3MB each.
Formats: doc, docx, pdf, ppt, pptx, xls, xlsx, txt.
Send request